

Paediatric and Neonatology Marketing Strategy for Hospitals in India
Last reviewed
Paediatric marketing in India speaks to parents, usually mothers, who search at odd hours, decide fast when a child is unwell and stay loyal for years when they trust a doctor. Win with round-the-clock access, named paediatricians, clear NICU capability and calm, practical content. Never use a child’s image or story without careful written consent from a parent.
Related: Healthcare Marketing Strategy Examples from India
This article is part of the healthcare digital growth series, best read in order from the pillar.
Updated 29 October 2026: merged in our guide on the parent as the real customer and added sections on the three parents to design for, the phone as front door, the maternity handover, children’s images and data under the DPDP Act, the visit experience and what to fix first.









Why paediatrics marketing is different
India has the world’s largest number of preterm births, about 3 million in 2020, and newborn mortality was 19 per 1,000 live births in 2021. That makes NICU capability a serious decision factor for parents choosing a maternity hospital, and urgent paediatric care a frequent search.
Paediatrics and neonatology marketing: a playbook for Indian hospitals
 1:53
Paediatric marketing speaks to parents, who search at odd hours, decide fast when a child is unwell, and stay loyal for years when they trust a doctor. Never use a child's image or story without careful written consent from a parent.
Read the transcript
Paediatric marketing speaks to parents, who search at odd hours, decide fast when a child is unwell, and stay loyal for years when they trust a doctor.
Never use a child's image or story without careful written consent from a parent.
India has the world's largest number of preterm births, which makes NICU capability a serious factor when parents choose a maternity hospital.
And urgent paediatric care is decided at night, on the phone.
During pregnancy, parents check NICU level and paediatric backup.
Fever or breathing trouble at night leads to urgent searches and calls.
Vaccinations and growth checks build a relationship that lasts years.
Round-the-clock paediatric emergency information on map listings and the website.
Paediatrician pages with qualifications, languages, timings and online booking.
And vaccination reminders on WhatsApp or SMS, with parental consent.
Start with real parent questions.
When does a child's fever need a doctor today?
What does a NICU level mean?
And what is the vaccination schedule?
The Infant Milk Substitutes Act bars promoting formula and foods for children under two, including through hospitals.
The Drugs and Magic Remedies Act lists stature, so no height-growth claims.
And never use a child's image without written parental consent.
Neonatal and paediatric care are covered under PM-JAY, and many parents have employer insurance.
Clear information on NICU costs per day helps families plan for a stressful stay.
The full guide, with sources, is on gauravphogat.com.
The link is in the description.
Key facts for paediatrics marketers
| Fact | Figure | Source |
|---|---|---|
| Preterm births in India (2020) | 3.02 million, the world’s highest | Lancet via ThePrint |
| Neonatal mortality rate (SRS 2021) | 19 per 1,000 live births | PIB |
| Infant mortality rate (SRS 2023) | 25 per 1,000 live births | Drishti IAS |
| Exclusive breastfeeding (NFHS-6) | 55.8%, down from 63.7% | NFHS-6 via ORF |
| PM-JAY coverage | Neonatal care, paediatric medicine and paediatric surgery are covered | NHA HBP 2.2 manual |
How patients decide
- Pregnancy. Parents check NICU level and paediatric backup when choosing a maternity hospital.
- Urgent illness. Fever or breathing trouble at night leads to urgent searches and calls.
- Routine care. Vaccinations and growth checks build a long relationship with one paediatrician.
- Specialist care. Referrals for paediatric surgery or subspecialties, where parents research carefully.
The parent is the real customer
A child never books an appointment, reads a review, calls the helpline at two in the morning or decides whether the bill was fair. A parent does all of that, usually worried, often tired and sometimes holding the patient. Yet many children’s services are marketed as if the child were the customer: cartoons, bright colours, smiling faces. That is fine on the ward. As a marketing strategy it misses the person making every decision.
In paediatrics the patient experiences the care and the parent experiences everything around it: finding the hospital, getting through on the phone, the wait, the explanation, the bill and the follow-up. A parent who felt listened to will forgive a long wait; one who felt dismissed will remember it for years, even if the clinical care was excellent. Parents talk constantly in school, housing society and family groups, so word of mouth is not a channel here, it is the channel. Paediatrics is also often a young family’s first real relationship with a hospital, and it can shape their choices for decades.
Three parents to design for
The parent at night
A child has a high temperature or is struggling to breathe. This parent is not researching. They need to know quickly whether you have a paediatric emergency service, how to reach it and whether someone will answer. Maps listings, the emergency number on the site and the first voice on the line matter more than any campaign.
The routine parent
Vaccinations, growth checks, a recurring cold, a school fitness form. This parent wants easy booking, short waits, a doctor who remembers the child and reminders for appointments the doctor has scheduled, and compares options on ease as much as reputation.
The parent managing a long-term condition
This parent becomes an expert in how the hospital works and needs continuity, a named person to call, clear records and a sense that the team knows their child. Every friction is felt again and again.
Most paediatric marketing speaks only to the routine parent. The other two carry more weight, because how a hospital treats a frightened parent at night, or a tired parent in the second year of a long condition, is what gets retold.
Channels that matter most
- 24×7 paediatric emergency information on map listings and the website.
- Paediatrician pages with qualifications, languages and OPD timings, plus online booking.
- Vaccination reminders on WhatsApp or SMS with parental consent.
- Parent education content on common illnesses, written calmly and reviewed by paediatricians.
- NICU pages that state capability factually, for expectant parents.
The phone is the front door
For most parents the phone call is the first real contact, and it is where many paediatric services fail: long holds, menu trees with no “my child is unwell” option, agents who cannot say which paediatrician is in today. I am cautious about automation here. Bots and voice menus handle routine bookings and reminders well, but they should never stand between a worried parent and a human. As I argue in when automation should not answer the phone, any automated path should make reaching a person obvious and immediate, and any sign of urgency should route straight to the clinical team as per the hospital’s protocol.
Agents on paediatric calls need specific training: how to speak to anxious parents, what they can and cannot say, and when to escalate. They never give clinical advice, and they always know how to get the parent to someone who can. That training is a brand investment, even if it sits in an operations budget.
Be found before the parent needs you
Most parents choose a paediatrician before they have an urgent reason to, usually around the birth, through the maternity team, a friend or proximity to home. After that, loyalty is strong, because parents do not like changing the doctor who knows their child. So the handover from maternity is one of the most valuable moments in paediatric growth: an introduction to your paediatricians before discharge, the first appointment booked with the parent’s agreement and the baby’s records already in place. Many hospitals leave this to chance and lose families exactly when they were easiest to keep.
For families who delivered elsewhere, visibility is local and practical: accurate maps listings for the paediatric OPD and emergency, detailed paediatrician profiles with timings, and talks by the paediatric team at schools or housing societies where appropriate. Parents look for a doctor near home whom other parents trust.
Content to publish first
Start with the questions patients and families actually ask. Each of these should open with a short, direct answer and be reviewed by a specialist before it goes live.
- When a child’s fever needs a doctor today
- What a NICU level means for parents
- The vaccination schedule explained
- Preparing a child for a hospital visit
- Feeding and growth: questions parents ask most
- Caring for a premature baby after discharge
The rules for this content are strict. Every clinical statement is written or approved by the paediatric team, content explains rather than diagnoses, and every piece tells parents when to contact a doctor. AI assistants are increasingly where parents ask their first question late at night, and clear, well-structured, specific pages are what they cite. The hospital should be a trusted source for those assistants, not a place that deploys a bot to answer clinical questions about children; I cover why in where AI belongs in the patient journey.
Compliance rules to know
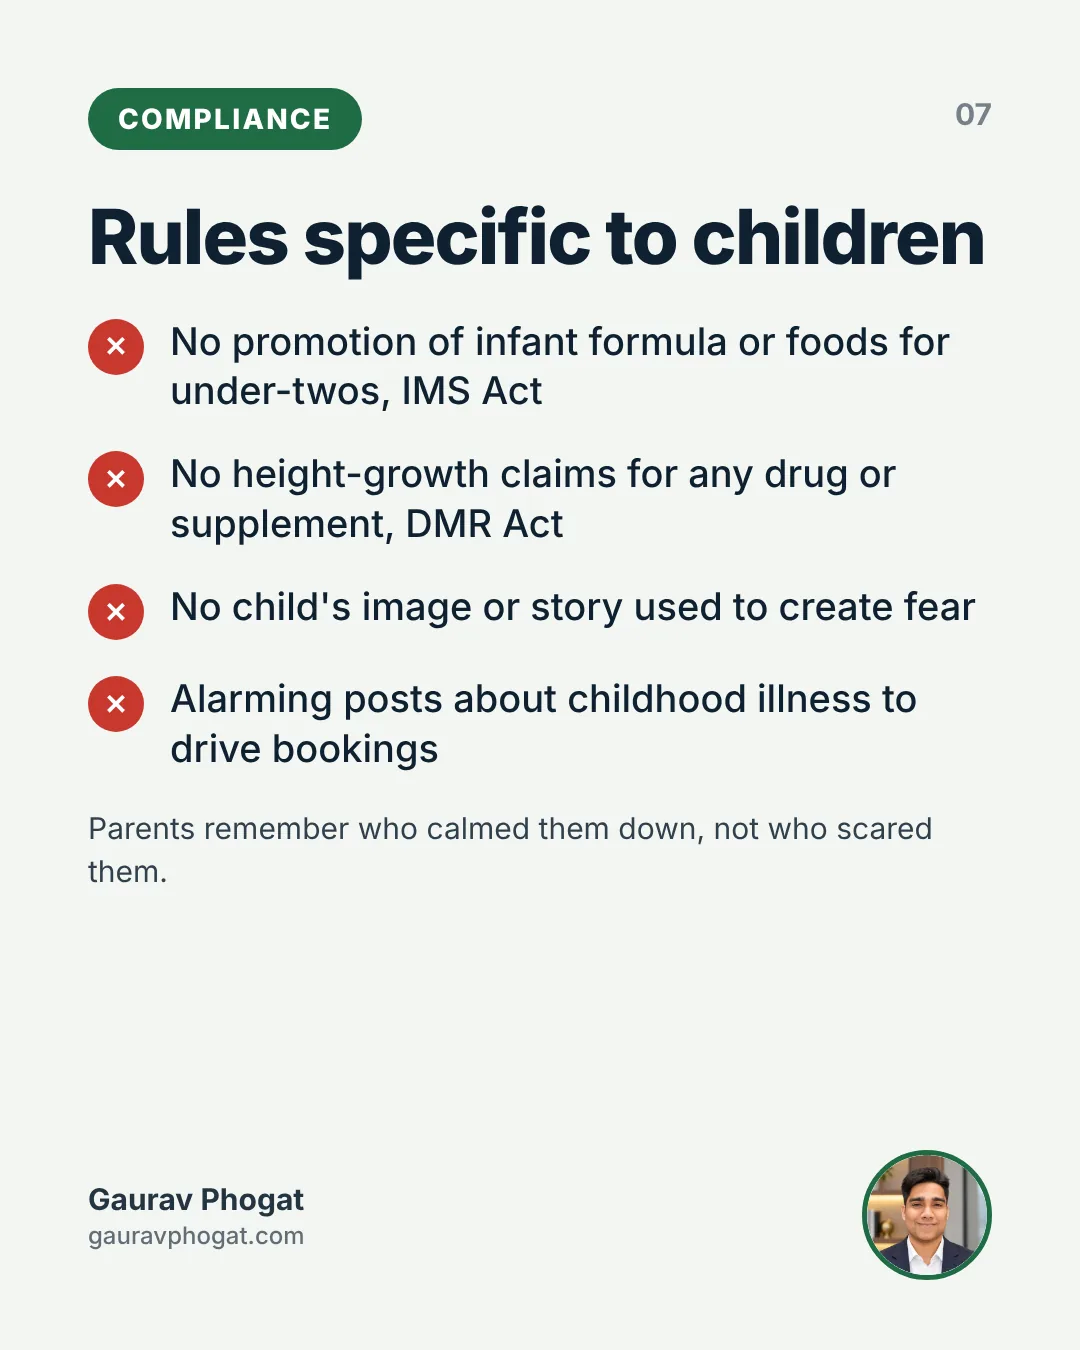
- The Infant Milk Substitutes Act, 1992 (amended 2003) bars promoting infant formula and foods for children under two, including through health facilities.
- The Drugs and Magic Remedies Act, 1954 lists ‘stature of persons’: no height-growth claims for any drug or supplement.
- Children’s images and stories need written parental consent and should never be used to create fear.
These sit on top of the rules that apply to every specialty: the Indian Medical Council (Professional Conduct, Etiquette and Ethics) Regulations, 2002, which remain in force after the NMC’s 2023 regulations were put in abeyance and treat soliciting patients as unethical; the CCPA’s 2022 guidelines on misleading advertisements; ASCI’s codes, including its 2025 rules for health influencers; and the DPDP Act, 2023 for every enquiry you collect. The regulation section of key statistics 2026 has the enforcement numbers, and DPDP notice and consent covers enquiry data.
Children’s images: default to none identifiable
The images that perform best on social media are often the ones a hospital should be most careful with. A child cannot consent, a parent’s consent given in an emotional moment may be regretted later, and images online do not go away. My default: no identifiable children in marketing unless there is a strong reason, written parental consent and review by someone outside the marketing team. Show the spaces, play areas and equipment, the doctors and nurses, parents’ hands rather than children’s faces, or illustrations. The hospital social media checklist includes the consent and image checks, and hospital social media marketing covers the wider principles. A service that is visibly careful with images tells parents it will be careful with their child.
Children’s data needs a higher bar
The DPDP Act requires verifiable parental consent for processing a child’s personal data and restricts tracking, behavioural monitoring and targeted advertising directed at children. Legal teams will interpret the detail, but the direction is clear: children’s data is not a marketing asset. The CRM should hold the relationship with the parent, in a household view linking parent and children, with consent recorded for the specific messages agreed. Keep vaccination and appointment reminders set by the paediatric team as service messages, send anything promotional only to the parent with consent, and never target anyone using a child’s health information. That is what a hospital CRM is actually for.
Insurance and government schemes
Neonatal and paediatric care are covered under PM-JAY, and many parents are insured through employer policies. Clear information about NICU costs per day and what affects them helps families plan for a stressful stay.
The visit, from the parent’s side
Walk through a visit as a parent and the brand moments are obvious. Is parking easy with a pushchair? Is there somewhere to feed a baby? Is there anything for a restless child, and does anyone explain delays? Does the doctor speak to the parent as a partner? Is the bill clear, and does the parent leave with a written summary of what to do next? Marketing does not run these things, but it can make the case for fixing them, because they drive what parents say to each other far more than advertising does. Parents’ reviews are unusually detailed and widely read; see why reviews are the hospital’s real front desk.
A short post-visit survey sent to the parent and reviewed monthly with the paediatric head and the operations lead is one of the cheapest, most useful tools a children’s service can have. It turns vague complaints into a list of fixable problems. Share the results, including the praise, with the front desk and nursing teams, who rarely hear what parents say about them.
What to measure
Judge marketing on outcomes the hospital can verify, not clicks. These are the numbers I would put on a monthly dashboard:
- Paediatric emergency calls answered, by hour
- Vaccination reminder opt-ins and completion
- Paediatrician retention: children returning for routine care
- NICU enquiries from expectant parents
- Parent review scores
Measure the relationship, not just the episode
Families who trust a hospital with their children often bring other care to it: maternity, adult consultations, grandparents’ treatment. Track how many paediatric families go on to use other services, and how quickly calls are answered at night and at weekends. Measuring paediatrics only on its own admissions and consultations understates what it contributes.
What I would fix first, in order
- Test the phone at different times, including nights and weekends, and fix the path from “my child is unwell” to a human voice.
- Check that maps listings, the website and every channel show the paediatric emergency service and number clearly and correctly.
- Review all marketing images and set a default of no identifiable children without written consent and independent review.
- Set up a household view in the CRM with proper parental consent, and separate service messages from promotional ones.
- Build a small library of clinician-approved content on the questions parents ask most, in the languages they use.
- Start a monthly post-visit survey and review it with the paediatric and operations leads.
None of this is glamorous. All of it treats the parent as the customer. Once those basics hold, campaigns have something solid to point to.
The common mistake
Using fear to drive bookings, such as alarming posts about childhood illnesses. Parents remember who calmed them down, not who scared them.
Questions people ask
Trust in a named paediatrician, round-the-clock access when a child is unwell, and for newborns, the level of NICU care available. Clear, calm information on these points does more than promotional campaigns.
No. The Infant Milk Substitutes Act bars promotion of formula and infant foods for children under two, including through health facilities. Hospitals should support breastfeeding information instead.
Only with written parental consent, for a clear purpose, and never in a way that creates fear or reveals medical details. Many hospitals use illustrations or staff photos instead.
It requires verifiable parental consent for processing children’s personal data and restricts tracking, behavioural monitoring and targeted advertising directed at children. In practice, hold the relationship with the parent, record consent for specific messages, separate service reminders from promotion and never target anyone using a child’s health information.
With trained agents who speak calmly, know what they can and cannot say, and escalate at once when a call sounds urgent, following the hospital’s clinical protocol. Agents never give clinical advice, and menus or bots should always offer a quick route to a person.
For logistics such as booking, directions, timings and documents, a well-governed assistant can help. Anything clinical about a child should go to the clinical team. The better role for AI is indirect: clear, clinician-reviewed content that external AI assistants can cite when parents ask questions at night.
Part of the specialty marketing strategies series. This guide covers marketing, patient communication and compliance; it is not clinical advice.
Related guides
- Digital marketing for doctors in India: a practical guide
- Healthcare marketing comparisons
- Treatment estimate and payer mix in the glossary
Sources
Read my takes first in Google Search
