

Maternity and Gynaecology Marketing Strategy for Hospitals in India
Last reviewed
Maternity and gynaecology marketing in India is a long relationship, not a single sale. Families choose a hospital early in pregnancy and judge it on trust, the doctor, safety and cost clarity, especially around C-section. Win with named doctors, honest package explanations, antenatal education and support across the whole journey. Never touch sex determination.
Updated 29 October 2026: merged in our guide on maternity as a brand relationship and added the family decision, the admission and discharge experience, post-birth follow-up, paid media and lifetime measures.
See every healthcare digital growth guide in one place.









Why obstetrics and gynaecology marketing is different
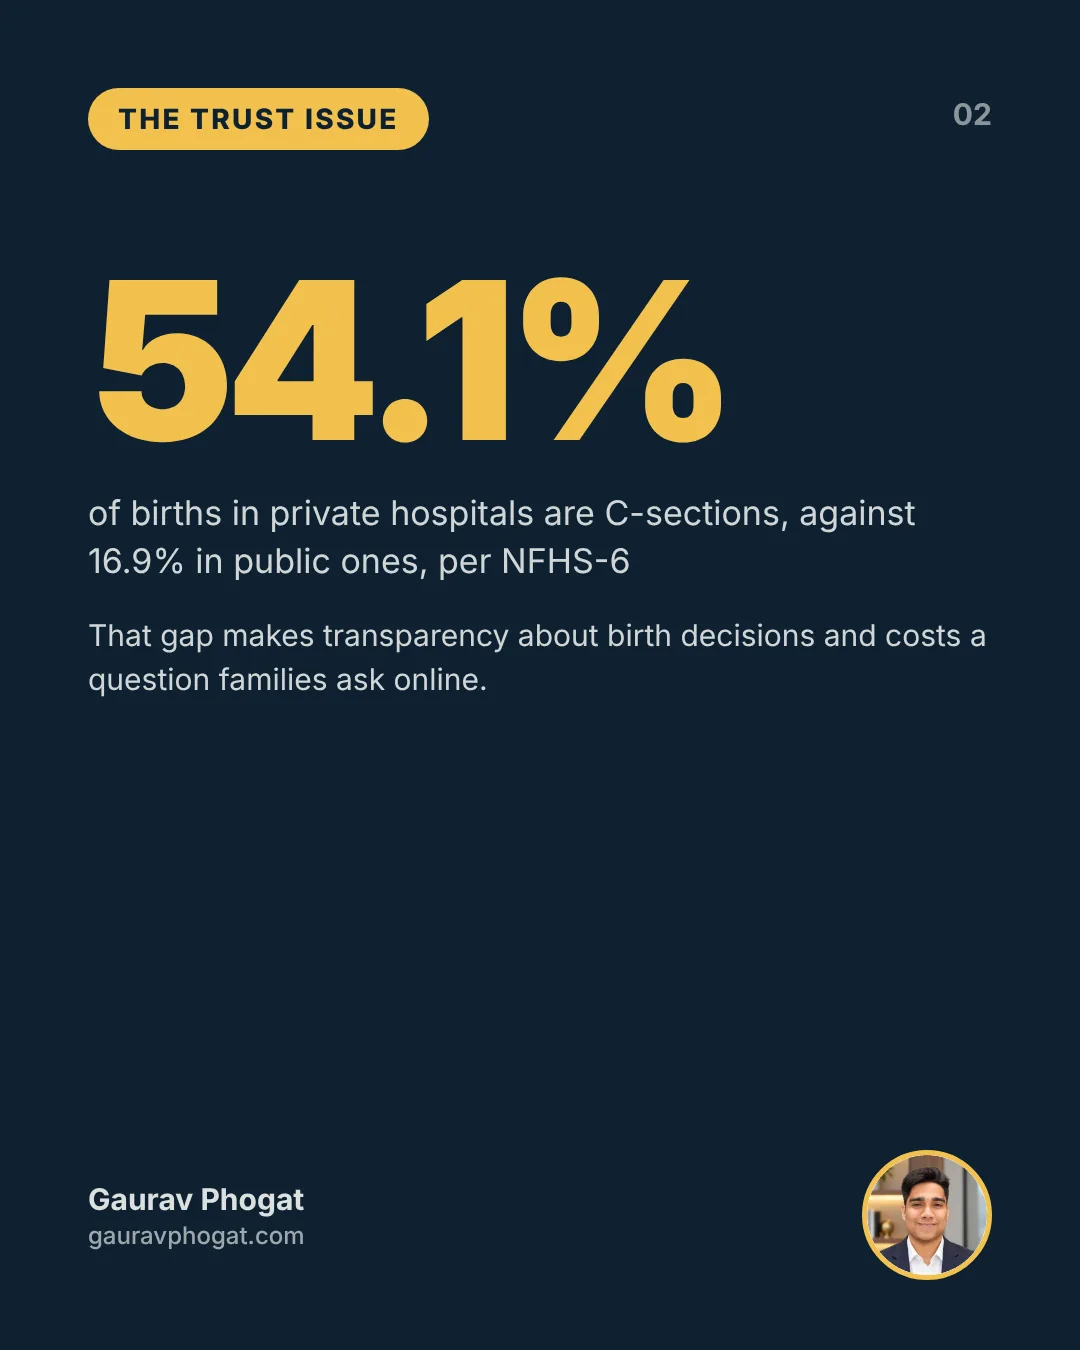
NFHS-6 (2023-24) found C-sections rose to 27.2% of births, at 54.1% in private hospitals against 16.9% in public ones. Institutional births are now over 90%. That gap makes transparency about birth decisions and costs a trust issue that families increasingly ask about online.
Obstetrics and gynaecology marketing: a playbook for Indian hospitals
 2:08
Maternity and gynaecology marketing is a long relationship, not a single sale. Families choose a hospital early in pregnancy and judge it on trust, the doctor, safety and cost clarity. Never touch sex determination. This version is updated for the NMC's advertising guidelines of October 2026.
Read the transcript
Maternity and gynaecology marketing is a long relationship, not a single sale. Families choose a hospital early in pregnancy and judge it on trust, the doctor, safety and cost clarity. Never touch sex determination. This version is updated for the NMC's advertising guidelines of October 2026.
National survey data show C-sections at fifty four percent of births in private hospitals, against seventeen percent in public ones. That gap makes transparency about birth decisions and costs a trust issue families increasingly ask about.
Couples search for gynaecologists and maternity hospitals near them, and ask friends. They compare doctors, facilities, NICU backup, packages and reviews. Then regular antenatal visits build the relationship that leads to delivery.
Doctor pages that show experience, languages, timings and backup such as anaesthesia and NICU. Maternity package pages that explain inclusions, exclusions and how costs change. And antenatal classes, which build relationships early.
Start with real questions. What should we ask when choosing a maternity hospital? What does a maternity package actually include? And how are decisions about delivery made?
The PCPNDT Act bans any advertisement of sex determination. Avoid any wording that could be read as offering it. Abortion care must protect the woman's identity. And under the NMC's guidelines of October 2026, patient stories cannot be used for promotion, even with consent.
Standard insurance wording excludes childbirth unless a policy adds maternity cover. Explaining packages and cover early prevents painful surprises at discharge.
The full guide, with sources, is on gauravphogat.com. The link is in the description.
Key facts for obstetrics and gynaecology marketers
| Fact | Figure | Source |
|---|---|---|
| C-section share of births (NFHS-6, 2023-24) | 27.2%, up from 21.5% | NFHS-6 via Drishti IAS |
| C-section rate in private vs public facilities | 54.1% vs 16.9% | NFHS-6 via ORF |
| Institutional births (NFHS-6) | 90.6% | NFHS-6 via Drishti IAS |
| Maternal mortality ratio (SRS 2019-21) | 93 per lakh live births | PIB |
Treat maternity as a relationship, not a package
I think most hospitals market maternity as if it were a single transaction. The campaign pushes a delivery package, the call centre quotes a price, the family books, the baby arrives and the room is cleared. On the P&L it is one admission. For the family it is one of the most emotionally loaded relationships they will have with any institution, and it runs for well over a year.
That gap between how the hospital counts it and how the family lives it is the opportunity. The delivery is the middle of the relationship, not the end of a sale. The months before shape the choice. The weeks after decide whether the family brings the baby back, returns for a second child and tells every relative who asks where to go. So the question for a growth leader is not “how do we sell more delivery packages” but “where in the whole journey are we losing the family’s trust”. Those questions lead to different budgets.
Everything in this guide is about brand, content, CRM and experience design. What happens clinically during pregnancy and birth belongs to obstetricians, neonatologists and nurses; marketing supports that work and never describes or promises it.
How patients decide
- Planning or early pregnancy. Couples search for gynaecologists and maternity hospitals near them and ask friends.
- Choosing the hospital. They compare doctors, facilities, NICU backup, packages and reviews.
- Antenatal care. Regular visits, scans and classes over months.
- Delivery. High emotion and high expectations, with family involvement.
- After birth. Postnatal care, paediatric follow-up and gynaecology care for years.
The choice is made early, and by the whole family
Families often settle on a hospital by choosing an obstetrician, and the doctor’s reputation, a friend’s recommendation and distance from home do most of the work. By the time a late-stage package campaign reaches them, many have already decided. Early visibility (being found when someone searches for obstetricians nearby, with warm, specific and current doctor profiles) matters more than late promotion.
The decision also involves more people than the expectant mother: partners, parents, in-laws and relatives who had a baby recently. In many Indian families the older generation’s comfort with the hospital carries real weight, so content that speaks only to the mother misses half the room. Reviews that describe the whole family’s experience matter here; I have argued that Google reviews are the hospital’s real front desk, and in maternity they are often the grandparents’ first impression.
What families are actually buying
A delivery package is a price, not a proposition. When I have listened to families explain their choice, they rarely talk about the package. They talk about feeling listened to by the doctor, not being rushed, whether the partner could stay, how clean the rooms were and whether the bill matched what they were told.
Price surprises at discharge are one of the fastest ways to lose a maternity family’s goodwill. Written estimates, an honest explanation of what could change the final amount and a respectful billing conversation do more for the brand than advertising. How far marketing can shape pricing depends on the hospital (I covered the limits in pricing in Indian private healthcare), but marketing can always insist that the promise in the ad matches the experience at the billing desk. Families are also buying reassurance: a hospital that explains clearly how to reach someone at night and what admission day looks like feels safer. Clarity is part of the product.
Channels that matter most
- Doctor pages with experience, languages, OPD timings and the hospital’s backup (anaesthesia, NICU).
- Maternity package pages that explain inclusions, exclusions and how costs change.
- Antenatal classes and webinars, which build relationships early.
- WhatsApp updates through pregnancy with explicit consent and the option to stop.
- Reviews collected after discharge through a compliant process.
Where paid media fits, and where it does not
Maternity still needs paid media, but with a narrower job. Paid search and map visibility should make sure the hospital and its obstetricians appear when a family in the catchment starts looking, early in the pregnancy. Social content should show the real people and spaces families will meet: nurses, the ward, the tour, the lactation support team.
Where I have seen maternity budgets go wrong is late-stage discount promotion aimed at families already booked elsewhere. They rarely switch, and the families who respond to a discount are the ones most likely to leave at the next price difference. A family choosing where to have a baby is not shopping for a deal. In my view most of the budget belongs in early visibility, doctor presence and content, with a smaller share for retention and follow-up; promotions, if used at all, belong to specific gaps such as a new unit families do not yet know.
Content to publish first
Start with the questions patients and families actually ask. Each of these should open with a short, direct answer and be reviewed by a specialist before it goes live.
- Choosing a maternity hospital: questions to ask
- What a maternity package includes, and what can change the cost
- Normal birth and C-section: how decisions are made, explained for families
- What to pack for the hospital
- Postnatal recovery: the first six weeks
- Gynaecology check-ups: what to discuss at each life stage
Plan content around the pregnancy calendar
Maternity is one of the few areas where a hospital can plan content around a known timeline. Early questions are about choosing a doctor and understanding visits, later ones about preparing for admission, and after delivery about feeding support, sleep and paediatric appointments. Content that arrives at the right month is useful in a way generic health content rarely is. The approach in healthcare content marketing applies directly, and the healthcare content calendar template helps map it across the months. Regional languages matter more here than almost anywhere, because the grandparents are reading too.
Classes, tours and parent groups
Antenatal classes, hospital tours and parent groups run by the clinical and nursing teams are among the strongest brand touchpoints a maternity service has. Families meet the people who will look after them and see the spaces before they need them. Marketing’s role is to make them easy to find and book, record attendance in the CRM and follow up with the information families asked for. They should never become sales events.
Admission and discharge are brand moments
The delivery admission is short, intense and remembered in detail for years: whether the desk was ready, whether someone explained what was happening, whether the partner or mother could stay, how the discharge felt. Marketing does not run any of this, but it has a stake in all of it.
- Pre-admission message or call that confirms paperwork, insurance and what to bring, so the family is not filling forms in a corridor.
- Discharge communication agreed with operations, because a slow or confusing discharge undoes goodwill built over months.
- A short survey or call after discharge, reviewed alongside clinical quality measures.
The link between these experience measures and revenue is real, and I made that case in what patient experience is worth on the P&L. In maternity it is clearer than in most specialties, because the family’s future choices depend on it.
After the baby goes home
Many hospitals go silent after discharge until the next bill. That is when the relationship is most fragile and most valuable. The family is tired and full of questions, the baby needs paediatric follow-up and the mother has her own.
- A WhatsApp line for non-urgent questions from new parents, answered by trained staff with clear escalation to the clinical team.
- Reminders for appointments the doctors have scheduled.
- Easy booking with the hospital’s paediatricians, with the baby’s records already in place.
- Invitations to parent groups run by the nursing team.
All of it needs consent under the DPDP Act, especially where it concerns a newborn, and an easy way to opt out. Done well, maternity becomes a gateway: a family that trusts the hospital with its baby’s early months tends to bring the grandparents’ check-ups, the partner’s care and the next pregnancy. Most hospitals never see this because they do not link records across specialties, so the value lands in other departments’ numbers and maternity gets managed as a cost centre with a discount lever.
Compliance rules to know
- PCPNDT Act, 1994 s.22: no advertisement of sex determination in any form. Avoid any wording that could be read as offering it, including ‘gender scan’.
- MTP (Amendment) Act, 2021 s.5A bars revealing the identity of a woman who has had a termination: no patient stories about abortion care.
- The Drugs and Magic Remedies Act, 1954 covers claims about miscarriage, contraception, menstrual and uterine disorders for drugs: no cure claims.
These sit on top of the rules that apply to every specialty: the Indian Medical Council (Professional Conduct, Etiquette and Ethics) Regulations, 2002, which remain in force after the NMC’s 2023 regulations were put in abeyance and treat soliciting patients as unethical; the CCPA’s 2022 guidelines on misleading advertisements; ASCI’s codes, including its 2025 rules for health influencers; and the DPDP Act, 2023 for every enquiry you collect. The regulation section of key statistics 2026 has the enforcement numbers, and DPDP notice and consent covers enquiry data.
Insurance and government schemes
Obstetrics and gynaecology is a PM-JAY specialty, but C-section, high-risk delivery and hysterectomy packages are reserved for public hospitals. IRDAI’s standard exclusion wording excludes childbirth unless a policy adds maternity cover, so many families pay directly or rely on employer maternity benefits.
What to measure
Judge marketing on outcomes the hospital can verify, not clicks. These are the numbers I would put on a monthly dashboard:
- Booking rate for antenatal registration
- Antenatal-to-delivery retention
- Package estimate requests and conversion
- Post-discharge review score
- Paediatric and gynaecology follow-up after delivery
Measure the lifetime relationship, not just admissions
If maternity is a relationship, it needs relationship measures alongside the monthly dashboard:
- Share of delivery families who book the hospital’s paediatric services in the following months.
- Share of families returning for a second delivery, tracked over the years it takes.
- Other family members who register at the hospital after a delivery.
- Experience scores at booking, admission and discharge, reviewed monthly with the service head.
- Where families first heard of the hospital, captured at the first visit rather than at admission.
Most of these need a CRM that links a mother, her baby and her family under one household record, with consent recorded properly. It is not technically hard, but it rarely exists because maternity and paediatrics often run separate systems. Fixing that link is one of the highest-value data projects for a hospital with a large maternity service, and a foundation for treating brand as a demand asset. Expect a mix of speeds: reviews and billing complaints improve within weeks of pre-admission messages and clearer estimates, paediatric bookings within months, and repeat deliveries take years.
Where I would start
Start by listening. Call a handful of families who delivered in the last few months and ask them to walk you through the experience from the first visit to the weeks after discharge. The moments where they felt unsure or let down are your plan.
Then fix the joins: link mother and baby records so the paediatric relationship begins automatically, set up a pre-admission message and a post-discharge check-in, make sure estimates are written and explained, and put a consent-based WhatsApp line in place for new parents. Only then look at campaigns. When the relationship holds together, modest visibility at the start of the journey goes a long way, because every family that comes through becomes a source of the next one. When it does not, a bigger campaign sends more families into the same gaps.
The common mistake
Advertising a low normal-delivery package without explaining what happens to cost if plans change. Families feel misled at discharge, and the review reflects it.
Questions people ask
Usually early in pregnancy, often in the first trimester, after comparing doctors, facilities and packages. Marketing should support that research with clear doctor information, package explanations and antenatal education.
Honestly and factually: explain how birth decisions are made, who makes them and how costs change. With private C-section rates far above public ones, transparency builds trust; avoid claims that imply one mode of birth is guaranteed.
Anything suggesting sex determination, which the PCPNDT Act bans. Abortion care must also protect patient identity under the MTP Act, so no patient stories. Medicine claims about miscarriage or contraception are restricted under the Drugs and Magic Remedies Act.
Partners, parents, in-laws and relatives who have had babies recently. In many Indian families the older generation’s comfort with the hospital strongly shapes the final choice, so content should speak to the whole family, including regional-language material for grandparents, and reviews that mention the whole family’s experience carry particular weight.
No. Classes, tours and parent groups should be run by the clinical and nursing teams for families’ benefit; they are strong brand touchpoints precisely because they are genuine. Marketing should make them easy to find and book, record attendance in the CRM and follow up with requested information.
How many delivery families go on to use the hospital’s paediatric services, how many return for a second delivery, and how experience scores are trending at booking, admission and discharge. Those answers show whether maternity is building a lasting family relationship or just generating admissions.
Part of the specialty marketing strategies series. This guide covers marketing, patient communication and compliance; it is not clinical advice.
Related guides
- Digital marketing for doctors in India: a practical guide
- Healthcare marketing comparisons
- Treatment estimate and payer mix in the glossary
Sources
- NFHS-6 via Drishti IAS
- NFHS-6 via ORF
- PIB
- Google Search Central: creating helpful, reliable, people-first content
- DPDP Rules, 2025 (Press Information Bureau)
Read my takes first in Google Search
