

50 ChatGPT prompts for hospital marketers (with review rules)
Last reviewed
The most useful ChatGPT prompts for healthcare marketing ask AI to structure, rewrite and analyse, not to supply clinical facts. Use anonymised inputs only, never patient data. Give the model a role, audience, constraints and approved facts, and ask it to flag uncertain statements. Every output then needs doctor review for clinical accuracy and a check against NMC, ASCI and ad platform rules.
Related: Hospital apps on the Play Store: what 50 Indian hospital apps and 827 reviews show
New to the topic? Start here: AI in healthcare operations sets out the reading order.
Related: ChatGPT for Marketers: A Practical 2026 Guide for Indian Teams
Updated 24 October 2026: merged in our guide on building a team prompt library, and added how to structure, test, review and maintain library entries.
Updated 11 October 2026 as per the NMC’s new advertising guidelines. Under the NMC’s Guidelines on Ethical Advertising and Public Communication, in force since 6 October 2026, doctors and hospitals can no longer request or share patient reviews or testimonials for promotion, use before-and-after photos or promotional patient stories (even with consent), offer discounts or other inducements, or make superiority or guaranteed-outcome claims. The advice below has been revised accordingly. See what the 2026 NMC guidelines allow.
Most hospital marketing teams in India now use ChatGPT or a similar assistant every day, usually without any shared rules. One person pastes in an enquiry transcript with a patient’s name in it; another publishes a symptom article with an invented statistic; a third writes ad copy promising “painless” treatment. None of them meant to break anything. They just did not have a list of good prompts or a checklist for what happens after the prompt.
This article gives you both. First, the rules your team should follow before using any public AI tool. Then 50 copy-ready prompts grouped by the work marketing teams actually do, each with placeholders in square brackets. Finally, how to write better prompts yourself and a review checklist for anything AI helps produce. If you are building this into a shared library, the section below on how to build and govern a team prompt library covers ownership, versioning, testing and access.







What rules should come before any prompt?
A prompt list without rules is how hospitals end up with privacy incidents and regulatory complaints. These are the five I would put on the wall.
1. No patient data goes into public AI tools
No names, phone numbers, UHIDs, reports, photographs, call recordings or chat transcripts that could identify a patient. That includes “just the first name and the condition”. On consumer ChatGPT, OpenAI states that content may be used to train its models unless you switch off the relevant setting, while business, enterprise and API products are not used for training by default. See OpenAI’s explanation of how data is used. Even with training switched off, the safest rule is simple: if it could identify a patient, it does not go in. Anonymise and aggregate first.
2. Treat DPDP as already in force
The Digital Personal Data Protection Act, 2023 and the DPDP Rules notified in November 2025 govern how personal data is processed, including by tools you use. Patients did not consent to their data being processed by an AI tool for marketing. The substantive obligations phase in by May 2027, but processes built now should already meet that standard. My guide to DPDP consent for hospital marketing explains the practical steps.
3. Every clinical statement is reviewed by a doctor
AI writes fluent, confident text, and it can be wrong about dosage, eligibility, risk and recovery. Anything that states a clinical fact must be reviewed and approved by a qualified doctor in that specialty before publishing, with the reviewer’s name recorded. The process is set out in how to review AI-generated doctor content.
4. Advertising and professional codes still apply
The Indian Medical Council (Professional Conduct, Etiquette and Ethics) Regulations, 2002 and the ASCI Code apply to the output, whoever or whatever wrote the first draft. No superlatives, no guarantees, no fear-based copy, no unsubstantiated claims. See NMC and ASCI rules for hospital advertising.
5. Label synthetic media where ASCI requires it
ASCI’s guidelines on labelling synthetically generated content, issued in September 2026, require disclosure where AI-generated or AI-altered visuals or audio could materially influence a consumer decision, such as AI avatars of doctors or cloned voices. Text drafted with AI help and routine edits do not need a label, but fabricated testimonials or results are not acceptable even with one. Read the ASCI guidelines and my summary of ASCI AI labelling rules.
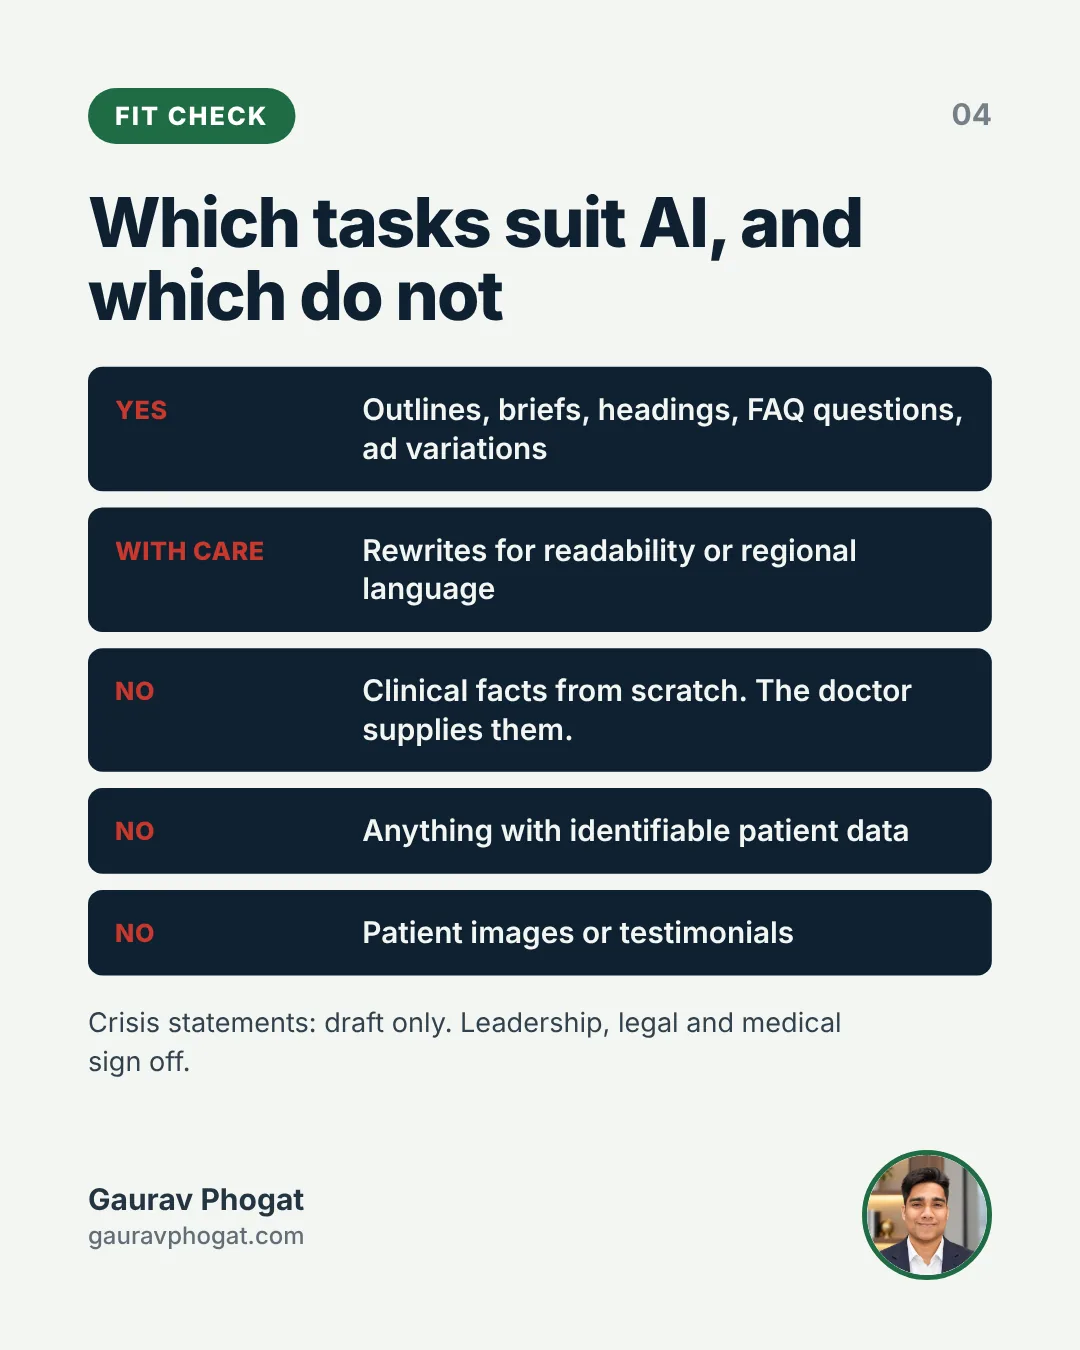
Which marketing tasks suit AI, and which do not?
| Task | Good fit for AI? | Review needed |
|---|---|---|
| Outlines, briefs, headings, FAQs (questions only) | Yes | Marketing editor |
| Ad headline and description variations | Yes | Marketing plus compliance check |
| Rewriting approved text for readability or regional language | Yes, with care | Doctor if clinical; native speaker |
| Summarising aggregated, anonymised reports | Yes | Analyst checks numbers |
| Writing clinical facts from scratch | No | Doctor must supply facts |
| Anything with identifiable patient data | No | Not applicable |
| Generating patient images or testimonials | No | Not applicable |
| Crisis statements | Draft only | Leadership, legal and medical |
These prompts cover the content stage. For where AI fits in the rest of hospital marketing, including search and GEO, paid media, enquiry handling, CRM and measurement, see AI in healthcare marketing: how hospitals in India use AI across the patient journey.
50 ChatGPT prompts for hospital marketers
Copy a prompt, replace everything in [square brackets], and add the context the model needs. Placeholders in double curly braces are for your messaging platform’s template variables and should be left as they are. All prompts assume anonymised inputs.
SEO and content briefs (prompts 1 to 10)
These work best with a clear page purpose and a doctor who will supply facts. For the bigger picture of planning, see healthcare content marketing.
- Keyword cluster for a service line. Act as an SEO strategist for a [multi-specialty hospital / single-specialty clinic] in [city]. List 30 search queries patients in India type about [specialty or procedure], grouped by intent: symptom research, treatment options, cost, doctor or hospital choice, and post-treatment. For each, suggest the page type that should answer it. Do not invent search volumes.
- Content brief for a procedure page. Write a content brief for a page on [procedure] at [hospital name], [city]. Include: target query, search intent, suggested H2 and H3 questions, the facts the treating doctor must supply (eligibility, preparation, duration, recovery, risks, fee range), internal pages to link, and a list of claims that must not be made. Leave every clinical fact as a placeholder for the doctor to fill.
- Outline from patient questions. Here are questions our front desk hears about [condition]: [paste anonymised list]. Turn them into an article outline with question-led H2s, ordered from most common to least. Flag any question that needs a doctor’s answer rather than general information.
- FAQ set for a doctor profile. Draft 8 FAQ questions patients ask before booking with a [specialty] consultant: timings, languages, fees, what to bring, follow-up, teleconsultation, insurance. Write questions only; we will fill answers from the hospital’s verified information.
- Title and meta options. Suggest 10 page titles (under 60 characters) and 10 meta descriptions (140 to 155 characters) for a page about [topic] in [city]. Avoid superlatives such as best, top, number one, guaranteed and painless. Use British spelling.
- Rewrite for readability. Rewrite this paragraph for a patient with no medical background, at roughly a Class 8 reading level, keeping every clinical fact exactly the same and adding nothing new: [paste approved text]. List any terms you simplified so the doctor can check them.
- Local page differentiation. We have location pages for [area 1], [area 2] and [area 3]. Here is the factual information for each: [paste facilities, timings, doctors, directions]. Suggest how to make each page genuinely different and useful, without duplicating text or creating thin content.
- Internal linking map. Here is a list of our page URLs and titles: [paste]. Suggest internal links from each page to 3 to 5 relevant pages, with natural anchor text. Point out orphan pages and pages that compete for the same query.
- Content gap check. Here are the H2 headings from our page on [topic]: [paste]. Here are headings from three pages ranking above us: [paste]. List the questions they answer that we do not, and the ones we answer better. Do not suggest copying their wording.
- Schema field list. List the structured data properties appropriate for a [Hospital / MedicalClinic / Physician] page, and which facts from our page should populate each. Output as a table. Do not generate values we have not supplied.
Social media and video scripts (prompts 11 to 18)
Short video works when a real doctor speaks plainly. Use AI to structure, not to replace the doctor’s voice. The free list of 50 reel hooks for doctors pairs well with prompt 11.
- Reel hooks. Write 15 opening lines (under 10 words each) for short videos where Dr [name], a [specialty] consultant, answers common patient questions about [topic]. No fear, no shame, no promises of results.
- 60-second explainer script. Write a 60-second script for Dr [name] explaining [procedure or condition] for patients: what it is, who it is for, what to expect, and when to see a doctor. Mark every clinical statement with [VERIFY] so the doctor can confirm it before recording.
- Myth versus fact post. Draft a carousel of 6 slides on common misconceptions about [topic]. For each myth, leave the fact as a placeholder [doctor to provide], and suggest a neutral headline. Avoid ridiculing anyone who believes the myth.
- Awareness day calendar. List health awareness days in India between [month] and [month] relevant to [specialties]. For each, suggest one post idea and one doctor video idea. Mark dates I should verify against the official source.
- YouTube description and chapters. Here is the transcript of our video: [paste]. Write a YouTube description (150 words), 5 chapter timestamps, and 10 tags. Do not add any claim that is not in the transcript.
- Repurpose a long video. Here is a 12-minute doctor talk transcript: [paste]. Suggest 5 clips of 30 to 60 seconds that stand alone, with the start and end lines for each and a caption for Instagram.
- Caption tone check. Review these 5 captions for a hospital Instagram account: [paste]. Flag anything that could read as fear-based, body-shaming, a guarantee, a superlative, or a call to self-diagnose. Suggest calmer rewrites.
- Regional language adaptation. Adapt this approved English caption into natural [Hindi / Telugu / Tamil / Marathi] for a general audience, not a word-for-word translation: [paste]. Keep medical terms in English where patients commonly use them. Note anything a native speaker should check.
Ads copy and keywords (prompts 19 to 26)
Keep the focus on searches that lead to appointments; my piece on keywords that book appointments explains the logic, and compliant ad copy for doctors covers tone.
- Search ad variations. Write 15 Google responsive search ad headlines (up to 30 characters) and 4 descriptions (up to 90 characters) for [specialty] consultations at [hospital], [area], [city]. Include location, timings, and booking options. No superlatives, no outcome claims, no prices unless I provide them: [price if any].
- Keyword intent sort. Here is a search terms report export: [paste anonymised CSV]. Group the terms into: likely to book, research only, job seekers, wrong service, wrong location, and competitor brand. Suggest negative keywords for the irrelevant groups.
- Negative keyword list. Suggest negative keywords for a Google Ads campaign promoting [service] at a hospital in [city], covering jobs, courses, free treatment, home remedies, government schemes we do not accept, and medicines. Explain any that are risky to exclude.
- Meta ad primary text. Write 5 versions of primary text (under 125 characters) and headlines for a Meta ad promoting a [health check package] at [hospital]. Neutral tone, factual inclusions only, no fear of illness, no before-and-after framing. Package facts: [paste].
- Landing page critique. Here is the text of our landing page for [service]: [paste]. Act as a patient deciding whether to book. List what is unclear, what is missing (fees, timings, doctor names, location), and where the page asks for too much information.
- Lead form questions. Suggest the minimum lead form fields for a [consultation booking] ad that lets our team call back, and explain why each is needed. Do not ask for symptoms, diagnosis or medical history in the form.
- Ad policy pre-check. Review these ad texts against Google and Meta healthcare advertising policies as you understand them: [paste]. Flag likely problems and say which policy area each relates to. I will confirm against the current policy pages.
- Sitelinks and callouts. Suggest 8 sitelinks with descriptions and 10 callouts for a [hospital] Google Ads account, using only these facts: [paste facilities, timings, services, insurance tie-ups].
PR and communications (prompts 27 to 32)
AI is useful for first drafts and preparation. Journalists still need real news, real quotes and verified facts. See how to write a hospital press release journalists use.
- Press release draft. Draft a press release about [event: new unit, new technology, doctor joining, camp]. Facts: [paste]. Use a news angle relevant to [city] readers, a quote placeholder for [spokesperson], and an editor’s note. No superlatives or firsts unless I supply proof: [proof].
- Media pitch email. Write a 120-word pitch email to a health reporter at [publication] offering Dr [name] as a source on [topic, e.g. monsoon infections]. Explain why it is timely and what the doctor can speak about.
- Spokesperson Q&A prep. List 15 questions a journalist might ask Dr [name] about [topic or announcement], including difficult ones about cost, access and safety. Do not write answers; we will prepare them with the doctor.
- Holding statement. Draft a short holding statement for [situation type, e.g. a social media complaint going viral] that acknowledges concern, confirms we are looking into it, protects patient confidentiality, and gives a contact. No admission of facts we have not verified.
- Internal announcement. Write an internal email announcing [news] to all staff, with what changes for them, who to contact, and what not to share externally yet.
- Op-ed outline. Outline an 800-word opinion article by Dr [name] on [public health topic in India]. Suggest a thesis, three arguments, and where data is needed. Mark every statistic as [SOURCE NEEDED].
Patient communication templates for WhatsApp and email (prompts 33 to 38)
Write templates, never individual messages containing patient details. Templates go through approval once, then your system fills the variables. Only message patients who have opted in.
- Appointment confirmation. Write a WhatsApp appointment confirmation template under 400 characters with placeholders for {{patient first name}}, {{doctor}}, {{date}}, {{time}}, {{location}} and a map link. Include how to reschedule. No medical advice.
- Pre-visit instructions. Draft a friendly email listing what to bring to a first [specialty] consultation: ID, previous reports, medicine list, insurance card. Leave any preparation instructions (fasting, etc.) as [doctor to confirm].
- Missed appointment follow-up. Write a polite WhatsApp message for patients who missed an appointment, offering to rebook without making them feel judged. Under 300 characters.
- Post-visit feedback request. Write a message asking for feedback after an OPD visit, with a link placeholder [feedback link]. It must not offer incentives for reviews or ask only happy patients.
- Health check reminder. Write a reminder for patients who opted in to annual health check reminders, mentioning that their last check was around [month] and how to book. Include an opt-out line.
- Regional language versions. Translate these 3 approved message templates into [language], keeping placeholders exactly as they are: [paste]. Keep the tone respectful and simple.
Analysis and reporting (prompts 39 to 44)
Paste aggregated tables, not raw lead lists. If a column could identify a person, remove it before the prompt.
- Monthly report narrative. Here is an anonymised, aggregated summary of this month’s marketing data: [paste table of sessions, enquiries, appointments, cost by channel]. Write a 200-word summary for the management team: what changed, likely reasons to check, and three questions to investigate. Do not invent causes.
- Funnel drop-off. Here are our monthly numbers by stage: [enquiries, contacted, appointments booked, appointments honoured, treated] for [months]. Calculate stage conversion rates and point out the biggest drop. Show your working.
- Campaign comparison. Compare these campaigns by cost per enquiry and cost per honoured appointment: [paste aggregated table]. Flag where the cheapest enquiries are not the cheapest appointments.
- Review theme analysis. Here are 100 public Google reviews of our hospital with names removed: [paste]. Group them into themes (waiting time, billing, doctor communication, cleanliness, parking, etc.) with counts and representative quotes.
- Search Console query analysis. Here is a Search Console export of queries for [page]: [paste]. Identify queries with high impressions and low click-through, and suggest title or content changes for each.
- Spreadsheet formula help. I have a Google Sheet with columns [list]. Write formulas to calculate [metric] by month and by channel, and explain each one.
Research and strategy (prompts 45 to 50)
AI is a thinking partner here, not a source. Any figure it offers must be traced to a real source before it reaches a deck.
- Catchment questions. We are planning marketing for a [specialty] unit in [area, city]. List the questions we should answer about the catchment (population, competing facilities, travel time, insurance mix, languages) and where in India such data is usually found. Do not guess the answers.
- Competitor content audit framework. Create a framework to compare our [specialty] content with 5 competitors on: topics covered, doctor visibility, video use, fee transparency, booking ease and update frequency. Output as a table template.
- Patient persona draft. Draft 3 patient personas for [service] in a Tier 2 city in India based on these interview notes: [paste anonymised notes]. Keep to what the notes support and mark assumptions.
- Launch plan skeleton. Outline a 12-week digital launch plan for a new [unit or clinic] in [city], covering website, Google Business Profile, search ads, doctor content, PR and referral outreach. Give tasks by week, not budgets.
- Stakeholder brief. Summarise this long strategy document for a hospital board in one page: [paste]. Keep the numbers exactly as given and list decisions required.
- Pre-mortem. We plan to [initiative]. Imagine it has failed after six months. List the 10 most likely reasons, grouped by people, process, data and compliance, and one early warning sign for each.
How do you make these prompts better?
The difference between a generic answer and a usable draft is almost always context. Six habits make the biggest difference.
- Give a role and an audience. “Act as an editor for a hospital website whose readers are first-time patients in a Tier 2 city” produces different text from a bare request.
- Supply the facts, ask for the structure. Paste the doctor-approved facts and ask the model to organise and simplify them. Never ask it to supply clinical facts.
- State constraints explicitly. Word limits, character limits, British spelling, banned words (best, guaranteed, painless, cure), reading level, tone.
- Ask for flags, not just answers. “Mark any statement you are unsure of with [VERIFY]” or “list assumptions” makes review faster and safer.
- Show an example. Paste one approved post or ad in your house style and ask for more in the same style.
- Iterate in the same thread. Ask for a shorter version, a warmer tone, or a version for a different audience rather than starting again.
Save the prompts that work, with notes on what changed, in a shared library. Over a few months the library becomes the team’s real asset. For how this fits into a wider AI plan, see generative AI in healthcare and the notes on keeping accuracy when producing medical content at scale.
How to build and govern a team prompt library
A list of prompts helps one person. A maintained library helps a team, because it takes the private habit and turns it into a shared asset: tested instructions for recurring tasks, with the brand context, the compliance guardrails and the review step written in. This is how I would build one, and how I would stop it going stale.
Why a library, and not just training
Training fades and people leave. A library stays, and it hands the newest executive what the team has learnt about getting good output for this brand, this audience and this regulatory setting on day one. It also changes review. When every AI-assisted piece comes from a known prompt, the reviewer knows what the tool was asked to do, what inputs it had and what it was told not to do. Review becomes checking against a standard rather than reading every draft with suspicion. And it gives you one place to write the rules, so they travel with every prompt instead of relying on memory.
What a single library entry should contain
The prompt text is the least durable part of an entry, because it changes as the tools change. The structure around it is what makes the entry useful.
- Name and purpose. One line on what the prompt is for and when to use it, such as turning a doctor interview transcript into a patient-facing article draft.
- Inputs required. What the user must supply: the transcript, the target reader, the department, the language, the approved key messages.
- Context blocks. Which shared blocks to include: brand voice, compliance rules, audience.
- The instruction itself. Written plainly, with the task, format and constraints.
- Output format. Length, structure, headings, tone, and what to flag rather than invent.
- Review route. Editor only, editor plus medical reviewer, or editor plus legal.
- Owner and version. Who maintains the entry, when it was last tested and what changed.
The review route is the field most teams forget and the one I would never skip. It turns the library from a productivity tool into a governance tool. A caption for a health camp and a condition explainer are not the same risk, and the entry should say so.
Write the brand down once, in context blocks
Most AI output is generic because the instructions are generic. Shared context blocks, reusable paragraphs pasted into prompts or loaded as standing instructions, give the biggest quality gain.
- Brand voice. Describe how the hospital sounds in concrete terms, not “warm and professional”, which every hospital claims. Short sentences. Plain words for conditions, with the medical term once in brackets. No exclamation marks. Speak to the patient and family, not to other doctors. A few examples of good and bad sentences help more than adjectives.
- Compliance and claims. What the output must never do: guarantee outcomes, compare clinical results with other hospitals, call a procedure painless or risk-free, name a patient, use before-and-after framing or give individual medical advice. Tell the model to flag any sentence that looks like a clinical claim instead of writing around it. Have the medical director and legal team approve this block.
- Audiences. Short descriptions of the patient searching for a condition, the family member arranging care for an elderly parent, the corporate HR buyer, the referring doctor and the international patient. Each entry then names its audience.
Which entries to build first
Do not build a library for everything. Start with tasks the team repeats every week where consistency matters, and turn the best prompts above into proper entries.
- Content repurposing: an approved doctor article into social posts, a WhatsApp broadcast, a newsletter paragraph and a short video script. The source is already reviewed, so risk is low and time saved is high.
- Drafting from interviews: a doctor conversation transcript into a structured first draft. The doctor’s own words are the source, and review goes back to the doctor.
- Translation and adaptation: approved content into regional languages, with a native reviewer. Adaptation helps most, but models make confident mistakes in medical terms.
- Operational writing: campaign summaries, agency briefs, meeting notes. Low risk, high volume, and a good place for new users to build confidence.
- Planning support: topic ideas from real patient questions, mapped to the healthcare content calendar template. The model proposes; the team decides.
Write the “what never goes in” rules at the top of the library and repeat them in onboarding. Beyond patient data, that includes unreleased business information such as unannounced launches, pricing decisions, doctor recruitment not yet public and board papers, in any tool not approved for it. And no entry should ask the model to write condition or treatment content from nothing; drafts start from a doctor’s interview, a reviewed page or clinician notes.
Test every prompt before it enters the library
A prompt earns its place by working reliably, not by looking clever. Run it several times with different real (anonymised) inputs and check the output: on brand, accurate to the source, in the right format, and flagging rather than inventing where information is missing.
Keep those test inputs with the entry. Language models change behaviour when they are updated, and a prompt that worked last quarter may start producing longer, flatter or more confident output. With saved tests you rerun the same inputs and compare; without them you only notice when a reviewer complains. I also ask for one “bad input” test per entry: give it an incomplete or messy source and see whether it asks for more or fills the gaps with plausible fiction. Prompts that invent under pressure do not belong in a healthcare library.
Review AI-assisted drafts against the source
A junior writer’s mistakes are usually visible. A language model’s mistakes are fluent: the sentence reads well and is slightly wrong, or it adds a reassuring phrase the source never said, or quietly turns “may help some patients” into “helps patients”. So reviewers read against the source, not just the draft. The entry says what the input was, so if it was a doctor’s interview, every factual sentence is checked against the transcript and anything that cannot be traced is cut or queried.
I ask that AI-assisted drafts are labelled as such inside the team, even when the published piece carries no label, so reviewers apply the right kind of attention. Review corrections then feed back into the library: if reviewers keep removing the same kind of overstatement, the compliance block or the prompt needs a sharper instruction.
Ownership, versions and keeping it alive
Libraries die of neglect. Someone builds a good shared document, the team uses it for a month, then people drift back to personal notes because the library did not keep up.
- Give the library an owner, usually the content lead, with protected time each month.
- Give every entry a named maintainer, often the person who uses it most.
- Log changes with a date and a reason. Mark retired prompts as retired rather than deleting them, so you can see what produced an older piece of content.
- Let anyone propose a new entry or improvement, with the owner deciding what goes in.
- Review the whole library each quarter: which prompts are used, which are ignored, and which produce the most review corrections. The corrections are the best signal of where a prompt needs work.
Where the library lives matters less than people think. A well-organised shared document or a simple internal page is enough, as long as there is one place, everyone knows where it is and it is kept current. Shared assets need owners, a point I make in building a digital team inside a hospital group, or they quietly become nobody’s job. For the wider governance principles, the WHO guidance on ethics and governance of artificial intelligence for health (2021) is worth a read, and McKinsey’s annual State of AI survey tracks how adoption is spreading.
Building the first version in a month
| Week | What to do |
|---|---|
| 1 | Ask everyone to share the prompts they actually use and the tasks they use them for. The messy, overlapping collection is your raw material, and it shows where AI use is already happening. |
| 2 | Write the three context blocks (brand voice, compliance, audiences) and get the compliance block approved by the medical director and legal. Confirm the “what never goes in” rules with IT and whoever handles data protection. |
| 3 | Turn the best existing prompts for your most important recurring tasks into full entries with inputs, format, review route and test cases. A small library people trust beats a large one they ignore. |
| 4 | Launch with a short session, not a long training programme. Show one or two entries working end to end, including review, and set the first quarterly review date before everyone leaves the room. |
The library becomes real the first time someone updates an entry because a reviewer caught a problem. That is the moment worth waiting for.
What should the review checklist include?
Every AI-assisted output should pass this before it is published or sent.
- Privacy: no patient-identifiable data was used in the prompt, and none appears in the output.
- Clinical accuracy: every clinical statement has been checked and approved by a named doctor in the relevant specialty.
- No invented facts: every statistic, date, award, ranking or study has a real source you have opened yourself.
- No superlatives or guarantees: no best, top, number one, guaranteed, painless, permanent, risk-free.
- No fear or shame: no copy that plays on anxiety about illness, ageing or body image.
- Hospital facts correct: doctor names, qualifications, timings, fees, addresses and phone numbers checked against the master record.
- Tone and language: plain, respectful, British spelling, regional language versions checked by a native speaker.
- Platform policy: ad text checked against current Google and Meta healthcare policies.
- Labelling: AI-generated or AI-altered visuals or audio labelled where ASCI guidelines require it, and fabricated content removed rather than labelled.
- Originality: no text copied from competitor pages; a plagiarism check on long-form content.
- Record kept: who prompted, who reviewed, and the date of approval, stored with the content.
Who reviews what?
| Output type | First reviewer | Final approver |
|---|---|---|
| Blog article or procedure page | Content editor | Treating doctor or department head |
| Social post or reel script | Social lead | Doctor featured |
| Search or Meta ad copy | Performance marketer | Marketing head, with compliance check |
| Press release | PR lead | Spokesperson and leadership |
| Patient message template | Patient experience lead | Operations head and doctor if clinical |
| Management report | Analyst | Marketing head |
Mistakes to avoid
- Pasting real enquiries to “save time”. Anonymise every time, or do not use the tool for that task.
- Trusting confident numbers. AI tools can produce plausible statistics that do not exist. If you cannot find the source, delete the number.
- Publishing on the same day. Build review time into the calendar. A 48-hour doctor review window is realistic for most teams.
- Letting AI pick the topic. Topics should come from patient questions, search demand and service priorities, not from what a model suggests.
- One prompt per person. Without a shared library, every marketer reinvents prompts and quality varies widely.
- Using AI images of patients or doctors. Synthetic “patients” and doctor avatars carry ASCI, trust and consent risks out of proportion to their value.
- Skipping regional review. Machine-generated regional language text can be grammatically fine and culturally off. A native speaker should read it.
How to measure whether AI is helping
Track a small set of measures for a quarter, comparing AI-assisted work with your earlier baseline:
- Turnaround time from brief to approved draft.
- Revision rounds needed before doctor approval. If AI drafts need more rounds than human drafts, your prompts or inputs need work.
- Error rate at review: clinical corrections, fact corrections and compliance flags per piece.
- Output performance: organic clicks, ad click-through rate, enquiry rate from pages, on the same basis as before.
- Privacy incidents: any instance of patient data entered into a public tool. The target is zero, and every incident should be logged and reviewed.
What good looks like: a shared, versioned prompt library; a written rule on patient data that everyone has read; a named doctor reviewer for each specialty; a content calendar such as the free healthcare content calendar template with review time built in; and drafts that reach approval in fewer rounds than before.
Where to start this week
Pick three prompts from this list that match work your team does every week, run them with anonymised inputs, and compare the drafts with what you would have written. Keep the ones that save time without adding review effort. Share the rules section with everyone who uses AI tools, including your agency. Prompts are easy to copy; the rules and the review habit are what keep a hospital’s name out of trouble.
Frequently asked questions
Sources and further reading
- OpenAI’s explanation of how data is used (help.openai.com)
- Indian Medical Council (Professional Conduct, Etiquette and Ethics) Regulations, 2002 (nmc.org.in)
- ASCI guidelines (ascionline.in)
- WHO guidance on ethics and governance of artificial intelligence for health (2021) (who.int)
- McKinsey’s annual State of AI survey (mckinsey.com)
Yes, for drafting, structuring, rewriting and analysis, provided no patient-identifiable data goes into the tool, every clinical statement is approved by a qualified doctor, and the final content follows NMC, ASCI and platform advertising rules. AI should support marketers and doctors, not replace their judgement or their review.
No. Names, phone numbers, conditions, reports or transcripts that could identify a patient should never go into public AI tools. Anonymise and aggregate data first, or use a business product your organisation has approved with appropriate data terms. Even then, avoid identifiable patient data unless there is a clear lawful basis.
ASCI’s synthetic content guidelines focus on AI-generated or altered visuals and audio that could materially influence a consumer decision, such as AI doctor avatars or cloned voices. Text drafted with AI help generally does not need a label, but it still has to be accurate, substantiated and reviewed like any other content.
A qualified doctor in the relevant specialty should approve any clinical statement, with their name and the review date recorded. A marketing editor should check tone, facts about the hospital and compliance with advertising rules. Ad copy should also be checked against current Google and Meta healthcare policies.
The most useful prompt asks for a content brief, not a finished article: target query, intent, question-led headings, the facts the doctor must supply and claims to avoid. The doctor then provides facts and the writer drafts. This keeps clinical accuracy with the doctor and structure with AI.
It can draft headline and description variations quickly. Give it only verified facts such as location, timings and services, ban superlatives and outcome claims in the prompt, and check every line against Google’s healthcare policy and Indian advertising codes before uploading. Expect to discard a share of suggestions.
Tell it not to include any figure you have not supplied, and to mark places needing data as source needed. Then verify any number that remains by opening the original source yourself. If you cannot find a source, delete the figure. Never publish a statistic only because the tool produced it.
Use it to draft message templates with placeholders, then have them approved once and sent through your messaging system to patients who have opted in. Do not use AI tools to write individual messages containing patient details, and keep clinical advice out of marketing templates entirely.
Yes. A shared, versioned library with owners, examples of approved outputs and notes on what works reduces quality variation between team members and agencies. Pair it with written rules on patient data and a review checklist so the library improves output without increasing risk.
Usually the content lead, with protected time each month. Each entry has a named maintainer, often its most frequent user. The medical director and legal approve the compliance context block, and IT or the data protection lead owns the rules on what data can go into which tools.
Assign an owner, log changes with dates and reasons, keep test inputs with each entry and review the library each quarter. Retire prompts rather than deleting them, fix the ones that cause the most review corrections first, and rerun tests whenever your AI tools are updated.
Share the brand voice, compliance and audience context blocks with agencies that draft with AI, so their output comes closer to your standard. Keep ownership of the library in-house, ask agencies to declare AI-assisted drafting, and apply the same review routes to their work as to your own team’s.
Read my takes first in Google Search
