

Hospital advertising rules in India: what ads can and cannot say
Updated on by Gaurav Phogat: added clause numbers from the official NMC PDF, a hospitals vs doctors table, the legal history, a trigger-word table and agency fee guidance. First revised on 11 October 2026 for the NMC advertising guidelines issued on 6 October 2026. ASCI figures checked against ASCI’s own press release. Every NMC 2026 resource on this site, including a copy checker and templates, is collected in the NMC 2026 compliance hub.
Hospital advertising in India is governed by overlapping rules, and they tightened on 6 October 2026, when the National Medical Commission issued guidelines on ethical advertising and public communication for doctors and hospitals. They cover social media, influencers, reviews and AI-generated content, and sit alongside the Drugs and Magic Remedies Act, consumer protection rules and ASCI’s code. The safe principle is now stricter: inform, do not promote. State facts about who you are, what you offer and how to reach you; drop testimonials, requested reviews, before-and-after images, discounts, unverifiable superiority claims and AI promotional campaigns.
See every healthcare PR and communications guide in one place.
This is a marketer’s overview, not legal advice. Have your legal or compliance team review campaigns before launch.
What changed on 6 October 2026: the NMC advertising guidelines
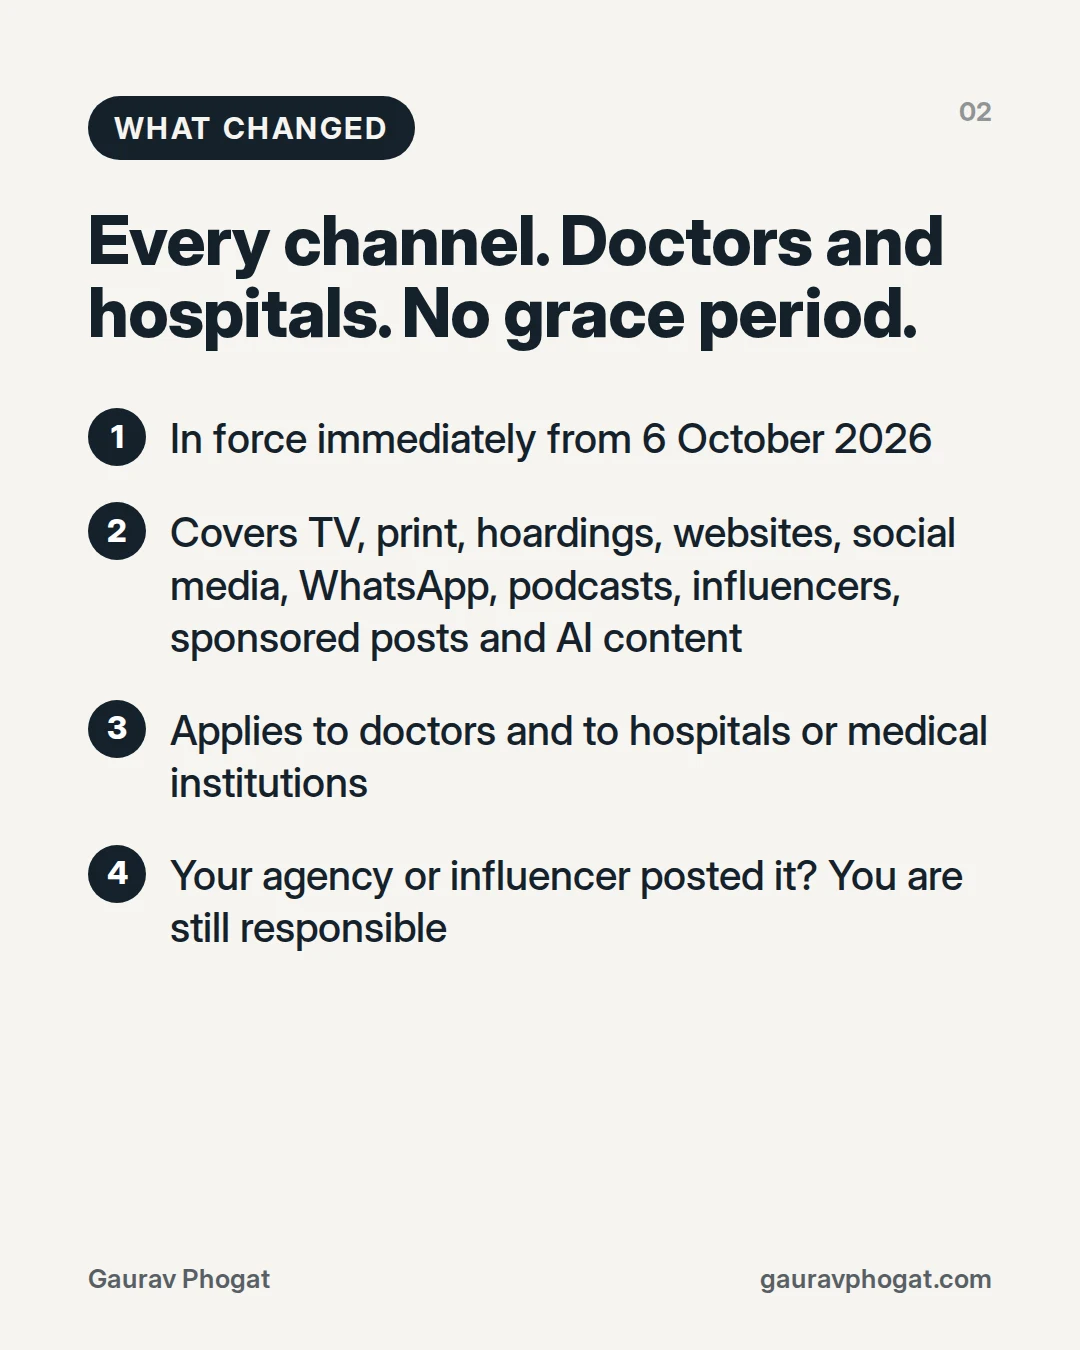
On 6 October 2026 the National Medical Commission’s Ethics and Medical Registration Board issued the Guidelines on Ethical Advertising and Public Communication by Hospitals/Medical Institutions and Registered Medical Practitioners. They came into force immediately and apply to doctors and to hospitals, across TV, radio, print, hoardings, websites, social media, WhatsApp and other messaging apps, podcasts, influencer and sponsored posts, online healthcare platforms and AI-generated content. The core shift: patient testimonials, requested reviews, before-and-after images, discounts and AI promotional campaigns are now explicitly off limits, and using an agency or influencer does not move the responsibility away from the doctor or hospital.
The guidelines were issued with reference to a Supreme Court writ petition, Writ Petition (Civil) No. 1160 of 2023, and operate under the existing 2002 medical ethics regulations. Hospitals are also governed by the Clinical Establishments Act or the relevant state law.
Read the exact text in the official NMC public notice (PDF): No. R-13014/01/2024-Ethics, dated 6 October 2026, issued by the NMC Ethics and Medical Registration Board and signed by Dr Raghav Langer, Secretary. Clause numbers on this page refer to that document.
What doctors and hospitals can still do
- Publish factual, verifiable information: name, location, contact details, departments, facilities, equipment, emergency services, accreditation and charges.
- Run a doctor directory with names, recognised qualifications, specialties, registration details and availability. This counts as patient information, not promotion.
- Create health awareness and educational content that does not promote a personal practice, solicit patients or get monetised through promotional marketing.
- Make factual announcements: starting a practice, a change of address or practice type, temporary absence, resumption, succession and consultation charges.
- Give public health talks in the doctor’s own name, and publish case studies in reputed medical journals.
- Use hoardings and billboards for factual information on infrastructure and facilities.
- Use best, top or leading only if the claim is objectively verifiable, with the award or ranking’s issuer, date and methodology disclosed (clause 8.1(ix)). “Best doctor” or “No.1 Specialist” style self-praise stays barred (clause 8.1(iii)).
- Use AI-assisted content that follows the guidelines, labelled as AI-generated or AI-assisted.
What is now off limits
- Requesting or sharing patient testimonials, recommendations or reviews for promotion. Patient consent does not, by itself, make them permissible.
- Before-and-after photos, promotional case studies, celebrity patients and success stories, except anonymised scientific or educational use.
- Fake, paid or manipulated reviews, ratings, followers or search rankings.
- Claims such as “Guaranteed cures”, “Best doctors”, “No.1 Specialist”, “100% success” or “painless treatment”, which clause 8.1(iii) names, and any best, top or leading claim that is not objectively verifiable (clause 8.1(ix)).
- Discounts, limited-period offers, contests, coupons, gifts and cashbacks that act as inducements. Factual disclosure of charges is still fine.
- Fear-based marketing and content that creates demand for unnecessary tests or procedures.
- Endorsing drugs, devices or products, paid or unpaid.
- Paying commissions, referral or lead-generation fees, or agency and influencer fees, linked to individual patients procured.
- AI-generated promotional campaigns for commercial interest, and AI that fakes a patient’s image, voice, testimonial or outcome.
- Identifiable patient details such as names and faces in public content.
Penalties
State Medical Councils enforce the guidelines for doctors, after a show-cause notice and a reasoned order, with appeals to the NMC’s Ethics and Medical Registration Board within 60 days. Hospitals face action under the Clinical Establishments Act or state law.
| Violation | Penalty for the doctor |
|---|---|
| First | Warning and mandatory ethics training |
| Second | Censure and a monetary penalty |
| Third | Registration suspended for 3 to 6 months |
| Serious, such as misleading cure claims, patient inducement or digital mass solicitation | Registration suspended for 6 to 12 months |
| Repeated | Removal from the medical register for 1 to 3 years |
What hospital marketing teams should do this month
- Audit live content: remove patient testimonial videos, review screenshots, before-and-after posts and success stories from websites, social media and ads.
- Stop review-request campaigns that ask patients to post reviews for promotion, including QR codes and WhatsApp nudges, until legal confirms what your institution may do.
- Pull every discount, offer, cashback and limited-period package promotion. Keep factual price lists.
- Rewrite superlatives. Replace best, No. 1 and painless with specific, verifiable facts.
- Make doctor content educational, and show the doctor’s name, qualifications and registration number on posts.
- Label AI-generated or AI-assisted content, and stop any AI-led promotional campaign.
- Review agency and influencer contracts so no fee is tied to patients or leads procured.
- Update your approval checklist and phrase library, and train the team and the agencies.
Sources: Medical Dialogues, MediaNama, The South First and Deccan Herald, reporting the NMC public notice of 6 October 2026. Check the notice on nmc.org.in for exact wording before acting on a specific case.










NMC's new advertising rules for doctors and hospitals (Oct 2026): what you can and can't post
 6:17
The National Medical Commission issued new advertising guidelines for doctors and hospitals on 6 October 2026, in force immediately. What you can still post, what is now off limits, the AI labelling rules, penalties and a clean-up checklist.
Read the transcript
On the sixth of October 2026, the National Medical Commission issued new guidelines on advertising by doctors and hospitals. They came into force the same day. This video covers what changed, what you can still post, what is now off limits, the rules on AI content, and the penalties. It is a marketer's summary, not legal advice.
First, the scope. The Guidelines on Ethical Advertising and Public Communication took effect immediately. There is no transition period. They cover TV, print, hoardings, websites, social media, WhatsApp and other messaging apps, podcasts, influencer and sponsored posts, online healthcare platforms and AI-generated content. They apply to registered doctors and to hospitals and medical institutions. And if an agency or an influencer published the content on your behalf, the responsibility still sits with the doctor or the hospital.
Now, what is still allowed. The theme is simple: facts a patient can verify. Your name, location, contact details and timings. Departments, facilities, equipment and emergency services. Accreditation, stated with its source. And charges, stated factually. Prices are fine. Offers are not, as you will see in a moment.
Doctors and hospitals can still inform and educate. A doctor directory, listing names, recognised qualifications, specialties, registration details and availability, counts as patient information, not promotion. Health awareness and educational content is allowed, as long as it does not promote a practice, solicit patients or get monetised through promotional marketing. Factual announcements are fine: starting a practice, a new address, a temporary absence, and consultation charges. And doctors can give public health talks in their own name, and publish case studies in medical journals.
Now the biggest change for marketing teams. Requesting or sharing patient testimonials, recommendations or reviews for promotion is not allowed. And patient consent, by itself, does not make a testimonial permissible. Before-and-after photos, promotional case studies, celebrity patients and success stories are out, except anonymised scientific or educational use. Patients must not be identifiable in public content. And fake, paid or manipulated reviews, ratings, followers or search rankings are prohibited.
Next, claims. Guaranteed cure is out. So is one hundred percent success. And painless treatment. Best doctor, number one, or any comparison you cannot objectively verify are also prohibited. An award or ranking can be mentioned only if it is independently verifiable, with the issuer, date and methodology disclosed.
Then, inducements. Discounts and limited-period offers that push people towards consultations, tests or treatment are prohibited. So are coupons, contests, gifts and cashbacks. Commissions, referral fees, and agency or influencer fees linked to the number of patients or leads delivered are not allowed. And doctors must not endorse drugs, devices or products, whether paid or unpaid.
The guidelines also address AI directly. Promotional content made with AI must carry a mark saying it is AI-generated or AI-assisted. AI-generated promotional campaigns for commercial interest are prohibited. AI must not be used to fake a patient's image, voice, testimonial or outcome. And any patient information fed into AI tools must comply with privacy and data protection law, including the DPDP Act.
Here is what compliant content looks like in practice. Instead of best knee surgeon, one hundred percent success, twenty percent off, say what the procedure is, who it suits, what recovery involves and what the risks are, with charges listed. Instead of a patient video, have the surgeon explain what recovery usually looks like. And instead of pushing patients for five-star reviews, keep your profile accurate and factual.
Now the penalties. State Medical Councils enforce them, after a show-cause notice. A first violation brings a warning and mandatory ethics training. A second brings censure and a monetary penalty. A third means suspension of registration for three to six months. Serious violations, such as misleading cure claims, patient inducement or digital mass solicitation, mean suspension for six to twelve months. Repeated violations can mean removal from the medical register for one to three years. Hospitals face action under the Clinical Establishments Act or state law.
So what should a marketing team do this week? Remove patient testimonials, review screenshots and before-and-after posts from your website, social media and ads. Pause campaigns that ask patients for reviews until your legal team confirms what is allowed. Pull every discount, offer and cashback, and keep factual price lists. Rewrite superlatives like best, number one and painless into specific, verifiable facts. And label AI content, and fix any agency or influencer contract that pays per patient or per lead.
The full written guide, with the penalty table, a pre-launch checklist and links to the sources, is on gauravphogat.com. The link is in the description. Check the NMC notice itself for exact wording before acting on a specific case.
Why this matters now
Healthcare is the sector India’s advertising self-regulator flags most often. Most problem ads now appear on digital platforms, and many breach the Drugs and Magic Remedies Act. For a hospital, a weak claim can mean a public ASCI ruling, regulatory attention and lasting damage to the trust that patients and referring doctors place in its name.
Healthcare is the sector the Advertising Standards Council of India flags most. In its 2023-24 annual complaints report, ASCI named healthcare the most violative sector, at 19 per cent of cases. Of the 1,575 healthcare advertisements it processed, 1,249 violated the Drugs and Magic Remedies Act, and 86 per cent of the healthcare ads appeared on digital platforms, according to ASCI’s press release. Hospital marketing has moved online, and scrutiny has followed.
The rules, in plain language
Four sets of rules overlap: medical ethics regulations administered by the National Medical Commission, now backed by its October 2026 advertising guidelines, which restrict doctors and hospitals from self-promotion; the Drugs and Magic Remedies Act, which bans claims to treat listed conditions; consumer protection law against misleading advertising; and ASCI’s self-regulatory code, which covers truthfulness, substantiation, comparisons and influencer disclosure.
| Rule | Who it applies to | What it means for hospital marketing |
|---|---|---|
| Medical ethics regulations (IMC Regulations, 2002, administered by NMC) | Registered doctors | Doctors should not solicit patients or advertise themselves. Doctor-led content needs care: educate, do not promote. |
| NMC professional conduct regulations, 2023 | Registered doctors | Notified in 2023 and then held in abeyance; the older rules continue to apply. An NMC panel has said norms for doctors and corporate hospitals should not differ. |
| NMC Guidelines on Ethical Advertising and Public Communication, 6 October 2026 | Registered doctors and hospitals or medical institutions | In force immediately. Bars testimonials and requested reviews for promotion, before-and-after images, discounts and offers as inducements, unverifiable superiority claims and AI promotional campaigns. Hospitals may publish factual, verifiable information. |
| Drugs and Magic Remedies (Objectionable Advertisements) Act, 1954 | Anyone advertising | Bans ads that claim to cure or treat specified diseases and conditions, and misleading ads about drugs and remedies. |
| Consumer Protection Act and CCPA guidelines on misleading ads, 2022 | Advertisers and endorsers | Claims must be truthful and substantiated; endorsements must reflect genuine experience and be disclosed. |
| ASCI Code and influencer guidelines | Advertisers, agencies, influencers | Claims need evidence; health influencers must disclose relevant qualifications; paid content must be labelled. |
| DPDP Act, 2023 | Anyone processing personal data | Retargeting, lead forms and WhatsApp follow-up need lawful, purpose-specific consent. |
Sources: ThePrint on the NMC panel, Drugs and Magic Remedies Act, ASCI influencer update.
Hospitals vs doctors: who the rules cover and who is penalised
The 2026 guidelines apply to both, but not in the same way. Doctors answer to their State Medical Council under the NMC Act. Hospitals answer to the authority under the Clinical Establishments Act or state law, which prevails over the guidelines in any irreconcilable conflict (clause 4.3). A doctor who authorised a hospital’s prohibited ad can still be examined personally (clause 11.5).
| Question | Doctors (RMPs) | Hospitals and medical institutions |
|---|---|---|
| Who enforces | State Medical Council, with appeals to the NMC EMRB (clauses 10.1, 11.1) | Authority under the Clinical Establishments Act or state law (clause 10.1 Explanation, 11.5) |
| Which law wins in a conflict | NMC Act, 2019 and 2002 Regulations (clause 4.2) | Clinical Establishments Act or state law (clause 4.3) |
| What they may publish | Formal announcements, education, talks in own name, journal case studies (clauses 8.2, 9.3) | Factual, verifiable information: name, location, departments, facilities, equipment, emergency services, accreditation, charges (clauses 8.3(i), 9.1) |
| Doctor listings | Own factual announcement of practice and fees (clause 8.2(ii)) | A website directory with names, qualifications, specialties, registration and availability counts as patient information, not advertising (clause 9.1) |
| Disclosure on posts | Own name, qualifications, registration status, SMR/NMR number (clause 3.2, Explanation III) | Name of the doctor with the same details (clause 3.2, Explanation IV) |
| Photos of doctors | Not where it is self-advertisement or solicitation (clause 9.2) | No promotional portrayal of an individual doctor (clause 8.3(ii)) |
| Superiority claims | “Best doctors”, “No.1 Specialist” barred (8.1(iii)); best, top, leading only if verifiable (8.1(ix)) | No comparative superiority claims (8.3(ii)); clause 8.1(ix) names hospitals too |
| Using agencies or influencers | No escape from responsibility (clause 4.4) | No escape from responsibility (clause 4.4) |
| Penalty | Graded: warning and ethics training up to removal from the register for 1 to 3 years (clause 10.1) | Penalty and appeal under the Clinical Establishments Act or state law (clause 11.5) |
How we got here: a short legal history
The 2026 guidelines close a gap that was argued in the Supreme Court for three years. Each date below is linked to its source.
- 2002: the Indian Medical Council (Professional Conduct, Etiquette and Ethics) Regulations bar doctors from soliciting patients and advertising themselves, but do not explicitly regulate hospitals (Cyril Amarchand Mangaldas analysis).
- 2 August 2023: the NMC publishes the Registered Medical Practitioner (Professional Conduct) Regulations, 2023, with new advertising rules (DT Next).
- 23 August 2023: the NMC holds the 2023 regulations in abeyance by gazette notification, and the 2002 regulations continue (DT Next).
- 10 October 2023: the Supreme Court issues notice to the NMC, the Union of India and the EMRB on a PIL by Dr Aniruddha Malpani seeking guidelines for advertising by corporate hospitals. The petition argued a regulatory gap: individual doctors cannot solicit patients under the 2002 regulations, but hospitals fall under the Clinical Establishments Act, over which the NMC had limited authority (LiveLaw).
- April 2024: an internal NMC panel says advertising norms for doctors and corporate hospitals should not differ, and prepares a report for the Supreme Court (ThePrint).
- 6 October 2026: the NMC issues the Guidelines on Ethical Advertising and Public Communication, covering doctors and hospitals, framed in view of Writ Petition (Civil) No. 1160/2023 (NMC notice).
One caveat: public reports cite the Malpani petition by its diary number, 34769 of 2023, and I could not confirm from public records that it is the same case as Writ Petition (Civil) No. 1160/2023 cited in the notice. The timing and subject match, but treat the link as likely rather than confirmed.
Primary sources: the NMC guidelines of 6 October 2026 (PDF), the Clinical Establishments (Registration and Regulation) Act, 2010 on India Code, and the Department of Consumer Affairs note on the CCPA Guidelines for Prevention of Misleading Advertisements and Endorsements for Misleading Advertisements, 2022, published on 9 June 2022.
What can hospital marketing safely say in India?
Hospitals can state verifiable facts: services offered, doctors’ qualifications and registration, facilities, timings, accreditation with its source, fees and how to book. Claims must be truthful, verifiable and free of superiority or outcome promises; since October 2026, patient testimonials and requested reviews are off limits for promotion, even with consent. Health information should be accurate, clinician-reviewed and free of cure promises for listed conditions.
- The hospital’s name, locations, specialties and services offered.
- Doctors’ names, recognised qualifications, specialties, registration details and availability, as a factual directory rather than promotional profiles.
- Facilities, technology and accreditations that are current and verifiable.
- Timings, contact details, how to book, and charges stated factually. Prices are fine; discounts and offers are not.
- Educational content on conditions and prevention, reviewed by clinicians and free of cure claims.
What should hospital ads avoid?
Avoid cure or guaranteed-outcome claims, superlatives such as “best” without independent proof, unverified success rates, fear-based messaging, before-and-after images and patient testimonials (barred for promotion even with consent since October 2026), discounts and limited-period offers, AI-generated promotional campaigns, undisclosed influencer payments, and any claim to treat conditions listed under the Drugs and Magic Remedies Act. If a claim cannot be evidenced, leave it out.
- “Cure”, “guaranteed”, “100 per cent success” or similar outcome promises.
- “Best”, “No. 1” or “only” claims without independent, current substantiation.
- Before-and-after images, patient testimonials, requested reviews and success stories, even with consent.
- Comparisons with named competitors you cannot prove.
- Doctor self-promotion framed as advertising rather than education.
- Influencer posts about treatments without disclosure and relevant qualifications.
- Retargeting based on sensitive health signals without clear consent.
- Discounts, limited-period offers, coupons, gifts and cashbacks used as inducements.
- AI-generated promotional campaigns, and AI that fakes a patient, voice or outcome.
- Agency or influencer fees tied to the number of patients or leads delivered.
What should a hospital check before any advertising campaign?
Before any campaign, confirm that every factual claim is true and documented, that nothing reads as a promise of outcome, that prices and inclusions are complete, that no testimonials, requested reviews, before-and-after images or discounts remain, that paid content is labelled, and that a clinician and a compliance reviewer have both signed off. Keep the approval record.
- Is every factual claim true today and documented?
- Could any line be read as a promise of outcome?
- Are prices, packages and inclusions stated fully?
- Have patient testimonials, requested reviews, before-and-after images and discounts been removed?
- Does every doctor-related post show the doctor’s name, qualifications and registration number?
- Is AI-generated or AI-assisted content labelled, and is nothing an AI promotional campaign?
- Is paid or influencer content clearly labelled?
- Has a clinician reviewed medical content and legal reviewed claims?
- Is consent in place for the data used to target or follow up?
For the consent side, see DPDP consent and hospital marketing and the DPDP consent notice template. For doctor content, see reviewing AI-generated doctor content.
Channel by channel
Each channel carries its own risk. Search ads drift toward superlatives and cure language, social posts toward before-and-after images and testimonials, influencer content toward undisclosed payment, and websites toward outdated claims. The practical control is a pre-approved headline and phrase library, plus clinical and legal review for any patient story or visual.
| Channel | Main risks | Practical control |
|---|---|---|
| Search ads | Superlatives in headlines, cure language, platform healthcare policies | Pre-approved headline library by service line |
| Social ads and posts | Before-and-after images, testimonials, sensitive health targeting | Clinical and legal review for any patient story or visual |
| Influencer content | Undisclosed paid posts, unqualified health claims | Written brief, disclosure label, qualification check |
| Website | Outdated claims, unreviewed medical content, unverifiable accreditation | Review dates and named reviewers on clinical pages |
| WhatsApp and SMS | Promotional messages without consent | Separate marketing consent and easy opt-out |
| Outdoor and print | Unsubstantiated “first” or “only” claims | Evidence file for every factual claim |
Words to handle with care
Some words reliably attract complaints. Cure, guaranteed, permanent, painless and risk-free promise outcomes. Best, number one, leading, only and first need current, independent proof. Miracle, breakthrough and revolutionary exaggerate. A success rate is acceptable only with a clear definition, source, period and context. When in doubt, describe the service rather than the result.
- Cure, guaranteed, permanent, painless, risk-free: promises of outcome. The NMC’s 2026 guidelines name guaranteed cures, 100% success and painless treatment explicitly.
- Best, number one, leading, only, first: need objective, independent verification under clause 8.1(ix). Any award or ranking needs its issuer, date and methodology disclosed. Doctor-centred phrases such as “Best doctors” and “No.1 Specialist” are named as barred in clause 8.1(iii).
- Miracle, breakthrough, revolutionary: exaggeration that invites complaints.
- Success rate: only with a clear definition, source, period and context.
Trigger words: risky phrase, why it fails, safe alternative
These are the phrases I see most often in hospital and clinic copy. Swap them before review, not after a complaint. Alternatives only work if the fact is true and documented.
| Risky phrase | Why it fails | Safe alternative |
|---|---|---|
| “Best doctor in Pune” | Named as barred in clause 8.1(iii) | “Dr A (example), MS (Orthopaedics), Reg. No. 00000, in practice since 2010” |
| “No.1 hospital in the city” | Superiority claim: needs an objectively verifiable ranking with methodology, date and issuer disclosed (8.1(ix), 8.3(ii)) | “Ranked in [named survey, year] by [issuer]; methodology linked”, or drop it |
| “Guaranteed results”, “guaranteed cure” | Named in 8.1(iii); guarantees also barred for hospitals (8.3(ii)) | “Results vary. Your doctor will explain what to expect.” |
| “100% success rate” | Named in 8.1(iii) | Drop it. Outcome data belongs in a reputed medical journal (8.2(i)) |
| “Painless treatment” | Named in 8.1(iii) | “Done under local anaesthesia” (if true) |
| “Miracle treatment”, “exclusive cure” | Named in 8.1(iii); unproven therapy rules in 8.1(vi) | Name the procedure and what it is used for |
| “10,000+ happy patients” | Advertising the number of patients treated (8.1(iii)) | “Department of Cardiology, established 2012” |
| “Flat 30% off”, “free consultation this week” | Inducement and limited-period offer (8.1(x)) | “Consultation fee Rs 800. Package includes A, B and C.” |
| “Don’t ignore this silent killer” | Fear-based marketing (8.1(i)) | “Common signs of high blood pressure, and when to see a doctor” |
| “Hear from our happy patients”, “rate us 5 stars” | Testimonials and review requests (3.2 Explanation V, 8.1(xi)); consent does not help (6.2) | Reply to reviews; ask for private feedback with no review link |
| “See the before and after” | Barred in 8.1(v) | Diagram or procedure explainer |
| “Most advanced technology in India” | Superiority claim about equipment (3.2 Explanation II, 8.1(ix)) | “3 Tesla MRI available 24×7” (if true) |
| “Recommended by Dr A” on a product | Product endorsement (8.1(iv)) | Explain the condition without naming products |
Agency and influencer fees: which models stay safe
Clause 8.1(vii) bars any commission, referral fee or lead-generation fee connected with procuring patients, and clause 8.1(viii) says agency, influencer and platform engagements must not be structured so that payment is linked to procuring or referring individual patients. Pay for work and media, not for patients.
Clause 8.1 sits under the heading for doctors, but clause 4.4 makes the doctor or institution answerable for anything it commissions, and clause 11.5 lets the council examine any doctor involved in a hospital campaign. My reading as a marketer, not legal advice:
| Fee model | Position | Why |
|---|---|---|
| Fixed monthly retainer | Safer | Not linked to patients |
| Project or deliverable fee (a website, 12 videos, a campaign) | Safer | Linked to output |
| Media spend plus a management fee on spend | Generally safer | Linked to spend, not to patients procured |
| Bonus on content or reach metrics (views, watch time, rankings earned honestly) | Safer, with care | Not patient-linked, but never reward bought engagement (8.1(xii)) |
| Cost per lead paid to the agency | High risk | “Lead-generation fee” is named in 8.1(vii) |
| Per appointment, per booking or per admitted patient | Not allowed | Payment linked to procuring individual patients (8.1(viii)) |
| Revenue share on patient billing | Not allowed | Consideration connected with patients (8.1(vii)) |
| Influencer paid per booking through a code or link | Not allowed | Patient-linked pay (8.1(viii)), and coupon codes are inducements (8.1(x)) |
Practical step: add a clause to every agency and influencer contract that no fee is calculated on patients, leads, bookings or billing, and that you approve all content before it goes live.
Building a review process
A workable review process has four parts: an evidence file for every recurring factual claim, a two-step sign-off with a clinician for accuracy and compliance for claims, a library of pre-approved phrases for each service line, and a record of every approval. Together they turn compliance from a bottleneck into a routine check.
- Keep an evidence file for every factual claim in regular use, with its date and source.
- Use a two-step sign-off: a clinician for medical accuracy and legal or compliance for claims.
- Keep a library of pre-approved phrases for each service line so teams do not improvise.
- Record approvals, so you can show what was checked if a complaint arrives.
- Review the library every six months, and whenever rules or guidance change.
If a complaint arrives
When a complaint arrives, respond within the deadline, pause the ad or post during review, check the evidence and correct or withdraw anything that cannot be substantiated. ASCI publishes its decisions, so a quick, cooperative response protects the hospital’s reputation far better than defending a weak claim in public.
Take it seriously and respond on time. Pause the ad or post while you review it, check the evidence, and correct or withdraw if needed. ASCI decisions are published, and quick, cooperative responses protect the brand far more than defending a weak claim.
Rules for AI-generated marketing content
Treat generative AI output as a first draft. Every factual and medical statement in AI-written ads or content goes through the same clinician and compliance review as human copy, nothing is published simply because a tool suggested it, and promotional content made with AI is labelled as AI-generated or AI-assisted, as the NMC’s October 2026 guidelines require. AI-generated promotional campaigns for commercial interest are not allowed at all.
Generative AI makes it easy to produce ad copy and health content at scale, and just as easy to produce claims nobody checked. Treat AI output as a first draft: every factual and medical statement goes through the same clinician and compliance review as human-written copy, and nothing is published because a tool suggested it. I cover the review process in reviewing AI-generated doctor content.
The NMC guidelines add three specific rules. Any AI-generated or AI-assisted promotional content must carry a mark saying so. AI must not be used to manipulate a patient’s image, testimonial, voice or clinical outcome, or to create synthetic endorsements. And patient information used as input to AI tools must comply with privacy and data protection law, including the DPDP Act and its 2025 Rules. Government public-interest campaigns are exempt.
Key statistics, with sources
ASCI’s own complaint data shows why hospital advertising needs a formal review process. Healthcare has led or ranked near the top of violative sectors across recent reporting periods, most of its violations involve claims under the Drugs and Magic Remedies Act, and nearly all problem ads now appear on digital platforms, especially Meta.
- Healthcare was the most violative sector in ASCI’s 2023-24 annual complaints report, making up 19% of cases, and 1,249 of the 1,575 healthcare advertisements it processed violated the Drugs and Magic Remedies Act, 1954. Source: ASCI, Annual Complaints Report 2023-24 press release, May 2024.
- In the first half of 2025-26, healthcare ranked third among violative sectors with 332 advertisements taken up, and 82% of the healthcare cases scrutinised violated the Drugs and Magic Remedies Act. Source: ASCI, Half-Yearly Complaints Report 2025-26 press release, November 2025.
- Digital media accounted for 97% of the advertising violations ASCI found between April and September 2025, with Meta platforms making up 78.9% of cases. Source: ASCI, Half-Yearly Complaints Report 2025-26 press release, November 2025.
Questions people ask
Yes, hospitals advertise widely, but claims must be truthful and substantiated, and ads cannot claim to cure conditions listed under the Drugs and Magic Remedies Act.
Not in a promotional sense. The NMC guidelines of October 2026 bar doctors from soliciting patients, self-promotion, testimonials and paid promotion; factual announcements and educational content that does not promote their practice are allowed.
They were notified in 2023 and then held in abeyance, so the 2002 regulations continue to apply. The NMC advertising guidelines of 6 October 2026 operate under those regulations and are in force.
Advertisements claiming to cure or treat specified diseases and conditions, and misleading claims about drugs and remedies.
Healthcare. In ASCI’s 2023-24 annual complaints report it was the most violative sector, at 19 per cent of cases, according to ASCI’s press release.
Not for promotion. Since 6 October 2026, NMC guidelines bar requesting or sharing patient testimonials, reviews and promotional patient stories, and patient consent does not make them permissible.
Only if objectively verifiable. Clause 8.1(ix) of the NMC guidelines allows best, top or leading claims only with a transparent, independent methodology, and any award or ranking must disclose its methodology, date and issuer. Doctor claims such as ‘Best doctors’ or ‘No.1 Specialist’ are barred outright under clause 8.1(iii).
Yes. ASCI’s 2023 update requires health influencers to disclose relevant qualifications and label paid content.
Yes. Misleading advertisement rules under the Consumer Protection Act apply to healthcare advertisers and endorsers.
Yes. Lead forms, retargeting and WhatsApp follow-up need lawful, purpose-specific consent.
Yes. Factual disclosure of charges is allowed, but discounts, limited-period offers, coupons, cashbacks and gifts used as inducements are barred under the NMC guidelines of 2026.
A clinician for medical accuracy and a legal or compliance reviewer for claims, alongside the marketing team.
No. It is a marketer’s overview. Hospitals should take legal advice on specific campaigns.
Guidelines on Ethical Advertising and Public Communication issued by the National Medical Commission on 6 October 2026, in force immediately, covering doctors and hospitals across all media including social media, influencers and AI content.
For doctors: a warning and ethics training for a first violation, censure and a fine for a second, suspension for 3 to 6 months for a third, 6 to 12 months for serious violations, and removal from the register for 1 to 3 years for repeated ones.
Only if it follows the guidelines and is labelled as AI-generated or AI-assisted. AI-generated promotional campaigns for commercial interest and synthetic patient endorsements are prohibited.
The authority under the Clinical Establishments Act, 2010 or the relevant state Act, with its own penalties and appeals (clauses 10.1 and 11.5). Any doctor who authorised or took part in the ad can also be examined by the State Medical Council.
No. Clause 8.1(vii) names lead-generation fees, and clause 8.1(viii) bars agency, influencer or platform payments linked to procuring individual patients. Retainers, project fees and media management fees are the safer models.
Read my takes first in Google Search
