

AI in Healthcare in India: Uses, Examples and Where It Works
Last reviewed
AI in healthcare in India now runs from AI-read chest X-rays in public TB screening to WhatsApp assistants that book appointments. Generative AI in healthcare is already useful in India, but mostly away from the diagnosis. The work that pays back today sits in the patient conversation (WhatsApp, chat and voice), in content and search visibility, in documentation support and in internal knowledge. Start where errors are cheap and reviewable, keep clinicians in charge of anything clinical, design for India’s languages and the DPDP Act from day one, and measure outcomes the CFO already tracks.
Related: AI-generated doctor content: where the review line sits
See every AI in healthcare operations guide in one place.
Related: Agentic AI in Healthcare: Use Cases for Indian Hospitals, and Where Not to Use It
Related: AI for Doctors in India: Practical, NMC-Safe Uses
Updated 29 October 2026: widened into a guide to AI in healthcare in India, with new sections on what it covers, uses and examples, healthcare chatbots, and risks and regulation (DPDP, ICMR, CDSCO, telemedicine rules).
Key takeaways
- The payback today is non-clinical: the patient front door (WhatsApp, chat and voice), content, AI search visibility, documentation support and internal knowledge.
- Keep clinicians in charge of anything clinical. Bots should route patients, not advise them.
- Tell patients when they are talking to software, and always offer a way to reach a person.
- Design for India from day one: mixed languages, WhatsApp and phone first, and the DPDP Act and Rules for consent and data.
- Start with a 90-day pilot and measure what the business already tracks: response times, appointments booked, calls handled and doctor hours returned.




What AI in healthcare covers
AI in healthcare is software that learns from data and then recognises, predicts, writes or talks inside the work of a hospital, clinic, lab or public health programme. In plain terms it does one of four jobs. It recognises patterns, such as a shadow on a chest X-ray. It predicts, such as how many beds will be free tomorrow. It generates, such as a draft discharge summary or a WhatsApp reply. Or it acts, such as booking a slot in a doctor’s calendar.
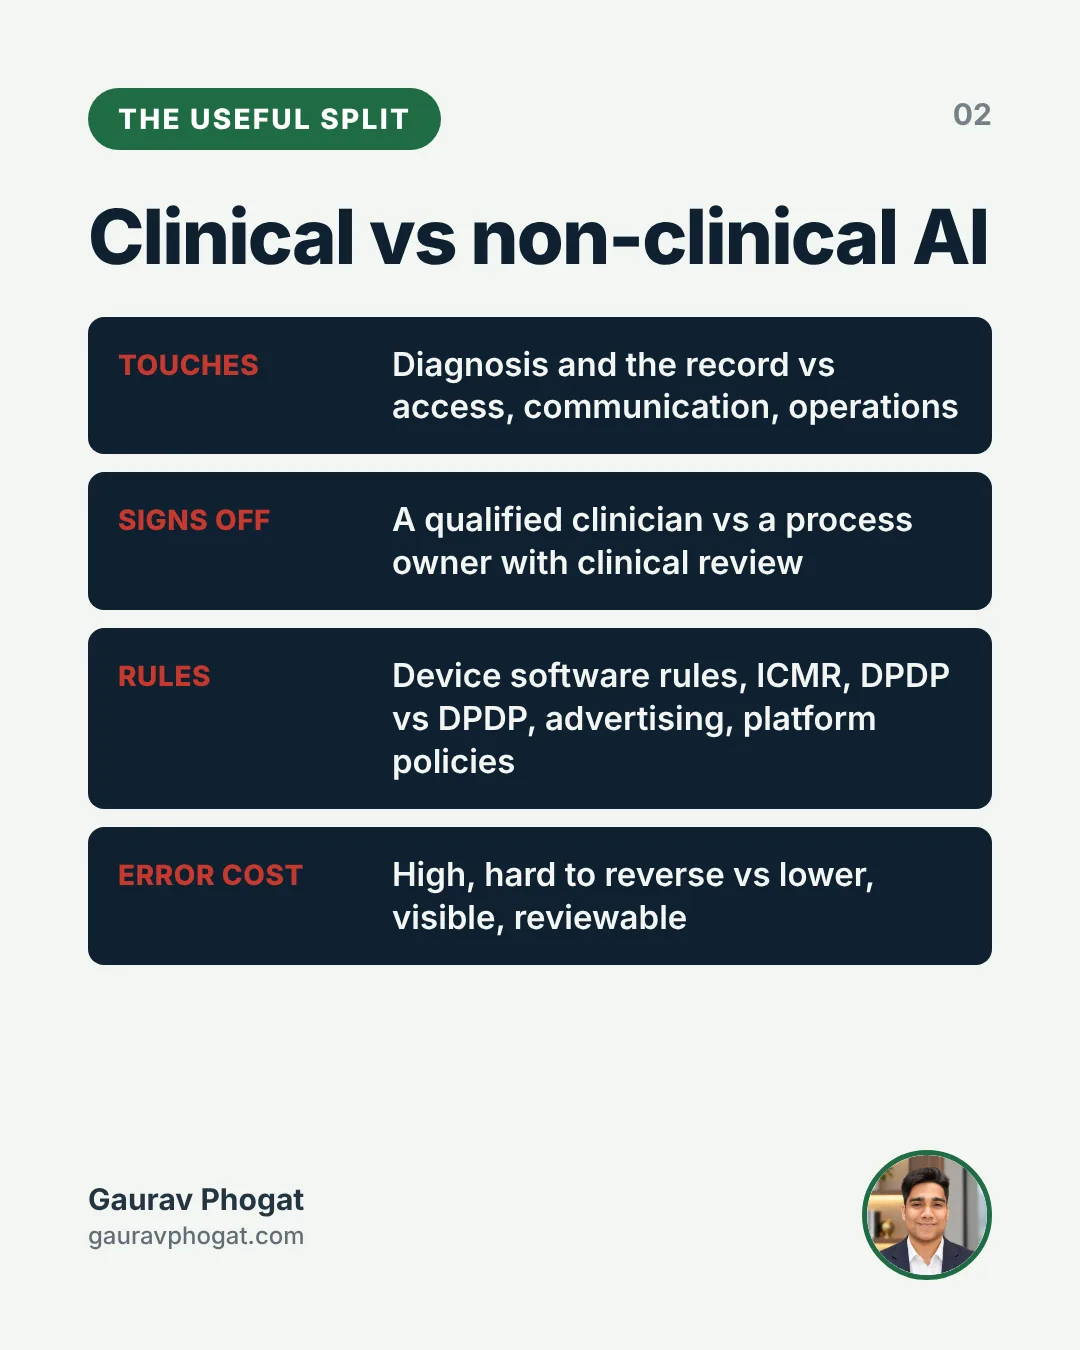
For anyone deciding where to start, the most useful split is clinical versus non-clinical. The two halves have different owners, different rules and very different costs of a mistake.
| Clinical AI | Non-clinical AI | |
|---|---|---|
| What it touches | Diagnosis, treatment, clinical triage and the medical record | Patient access, communication, content, operations and administration |
| Typical examples | Support for reading scans, flags on deteriorating patients, draft clinical notes | Answering timings and directions, booking, call summaries, bed and roster planning, content drafts |
| Who signs off | A qualified clinician, every time | A process owner, with clinical review wherever content touches health |
| Rules that apply | Medical device software rules, ICMR ethical guidelines, professional conduct rules, DPDP | DPDP Act and Rules, advertising rules, platform policies |
| Cost of an error | High and often hard to reverse | Usually lower, visible and reviewable |
I work on the digital, product and brand side of hospitals, so this guide explains clinical AI at the level a manager or marketer needs. It is not clinical advice and nothing here tells anyone how to diagnose or treat. For the non-clinical half, a non-clinical risk framework for AI in hospital operations sets out how I grade projects before anything goes live.
Generative AI in healthcare: where it works in India today
 2:28
Most hospital AI used to be predictive: scoring a scan or forecasting bed demand. Generative AI is different. It writes, talks and summarises. That makes it good at conversation, drafting and search, and unreliable wherever a confident wrong answer could hurt someone.
Read the transcript
Most hospital AI used to be predictive: scoring a scan or forecasting bed demand.
Generative AI is different.
It writes, talks and summarises.
That makes it good at conversation, drafting and search, and unreliable wherever a confident wrong answer could hurt someone.
Here is where it pays back in Indian hospitals today.
The patient front door: answering logistics on WhatsApp and chat, in several languages, and routing enquiries.
The contact centre: summarising calls and helping agents find answers.
Content and AI search: drafting patient information for clinician review.
And documentation support and internal knowledge, with a human checking the output.
And where it should not go yet.
Diagnosis or treatment advice from a general-purpose model without a clinician in the loop.
Unsupervised medical answers on chat or voice.
Route, do not advise.
Anything that hides the human.
Patients should know when they are talking to software.
And personal health data in tools whose data handling you do not control.
Three things make Indian deployments different.
Language.
Patients switch between English, Hindi and regional languages, often in one message.
Channel.
WhatsApp and the phone carry far more of the conversation than web forms.
And regulation.
The DPDP Act and its Rules shape consent, notice and retention.
A ninety-day way to start.
Weeks one and two.
Pick one problem with a number attached, such as unanswered WhatsApp enquiries after eight at night, and record the baseline.
Weeks three to six.
Build a narrow pilot with a clear handover to humans and reviewed scripts.
Weeks seven to ten.
Run it on real traffic and review conversations every week.
Weeks eleven to thirteen.
Compare with the baseline, then scale, fix or stop, and write down why.
Measure what the business already tracks: enquiries answered on time, appointments booked, calls handled without a callback.
Avoid vanity measures such as messages sent.
The full guide, with sources and checklists, is on gauravphogat.com.
The link is in the description.
Uses of AI in healthcare in India, with examples
These are the main uses of AI in healthcare I see in Indian hospitals and public programmes, from the most clinical to the least. Each comes with an example and the one question I would ask before signing a contract.
1. Imaging and diagnosis support
The oldest and most researched use: software that reads chest X-rays, CT scans, retinal images or pathology slides and flags what a radiologist or doctor should look at first. The word that matters is support. The tool prioritises and highlights; a qualified doctor reads, decides and reports.
Example: India’s National TB Elimination Programme uses AI to read chest X-rays. In March 2025 the Ministry of Health told the Rajya Sabha that an AI chest X-ray tool, DeepCXR, had been adopted by the programme and deployed in eight states and Union Territories, alongside AI-enabled handheld X-ray units, and that these tools were validated by ICMR (report).
Question to ask: has the tool been validated on Indian patients and the machines you actually use, and is it registered with CDSCO where the medical device software rules require it?
2. Clinical documentation
Ambient and dictation tools listen to a consultation, or take a doctor’s voice notes, and draft the note, discharge summary or referral letter for the doctor to edit and sign. The payback is doctor time. The risk is an error that quietly enters the medical record. Ambient documentation in the consultation room lists what to settle before a pilot.
Question to ask: who checks every draft, and does the record show that it was drafted by software and approved by a named doctor?
3. Chatbots and patient access
WhatsApp assistants, website chat and voice bots answer questions on timings, directions, doctor availability, published prices and report status, book appointments and route everything else to people. In India this is where most patients first meet hospital AI, because WhatsApp and the phone carry most enquiries. The section on healthcare chatbots below covers what they should and should not do.
Question to ask: what share of conversations end with the patient’s task done, not just with the bot closing the chat?
4. Hospital operations
Forecasting admissions and bed demand, rostering, operation theatre scheduling, claims and billing checks, inventory, and summarising contracts and policies. None of these touch a diagnosis, which makes them sensible first projects and the easiest to measure. Measuring an AI project when nothing clinical is being claimed gives the template I use.
Question to ask: which number on the operations dashboard will move, and who owns it?
5. Drug discovery and research
At the research end, AI helps screen candidate molecules, predict protein structures, design trials and find eligible participants for studies. For most Indian hospitals this is a partner activity with pharma companies, academic centres or research councils rather than something to build in-house. Research use falls under ICMR’s ethical guidelines for AI, covered in the regulation section below.
6. Content, search and internal knowledge
Drafting patient education for doctor review, being cited correctly by AI search, and helping staff search policies and SOPs. These are generative AI uses and are detailed in the next sections. For content, the review model in AI medical content at scale without losing accuracy is the one I follow.
AI in healthcare examples at a glance
| Use | Example in India | Who signs off | Risk level |
|---|---|---|---|
| Imaging and diagnosis support | AI reading of chest X-rays in TB screening | Radiologist or treating doctor | High |
| Clinical documentation | Draft consultation notes and discharge summaries | Treating doctor | High |
| Chatbots and patient access | WhatsApp booking, report status, enquiry routing | Front office lead, with clinical rules for routing | Medium |
| Hospital operations | Bed demand forecasts, rosters, claims checks | Operations head | Low to medium |
| Drug discovery and research | Molecule screening, trial matching | Principal investigator and ethics committee | Varies |
| Content and AI search | Patient education drafts, AI search visibility | Named reviewing doctor | Medium |
Where each of these sits, from the first search to follow-up, is mapped stage by stage in where AI belongs in the patient journey.
What generative AI in healthcare actually means
Most hospital AI until recently was predictive: a model scores a scan, flags a risky patient or forecasts bed demand. Generative AI is different. Large language models and their voice and image cousins produce new text, speech and summaries. That makes them good at conversation, drafting and search, and unreliable wherever a confident wrong answer could hurt someone.
Two newer terms matter. Conversational AI is generative AI wrapped in a chat or voice interface, the kind patients meet on WhatsApp or the phone. Agentic AI goes a step further: the system plans and takes actions, such as checking a doctor’s calendar and booking a slot. Each step up adds value and adds risk, so the governance has to step up with it.
I write about this from the digital, product and brand side of hospitals, not the clinical side. Everything below is about non-clinical use, or clinical-adjacent use where a clinician signs off.
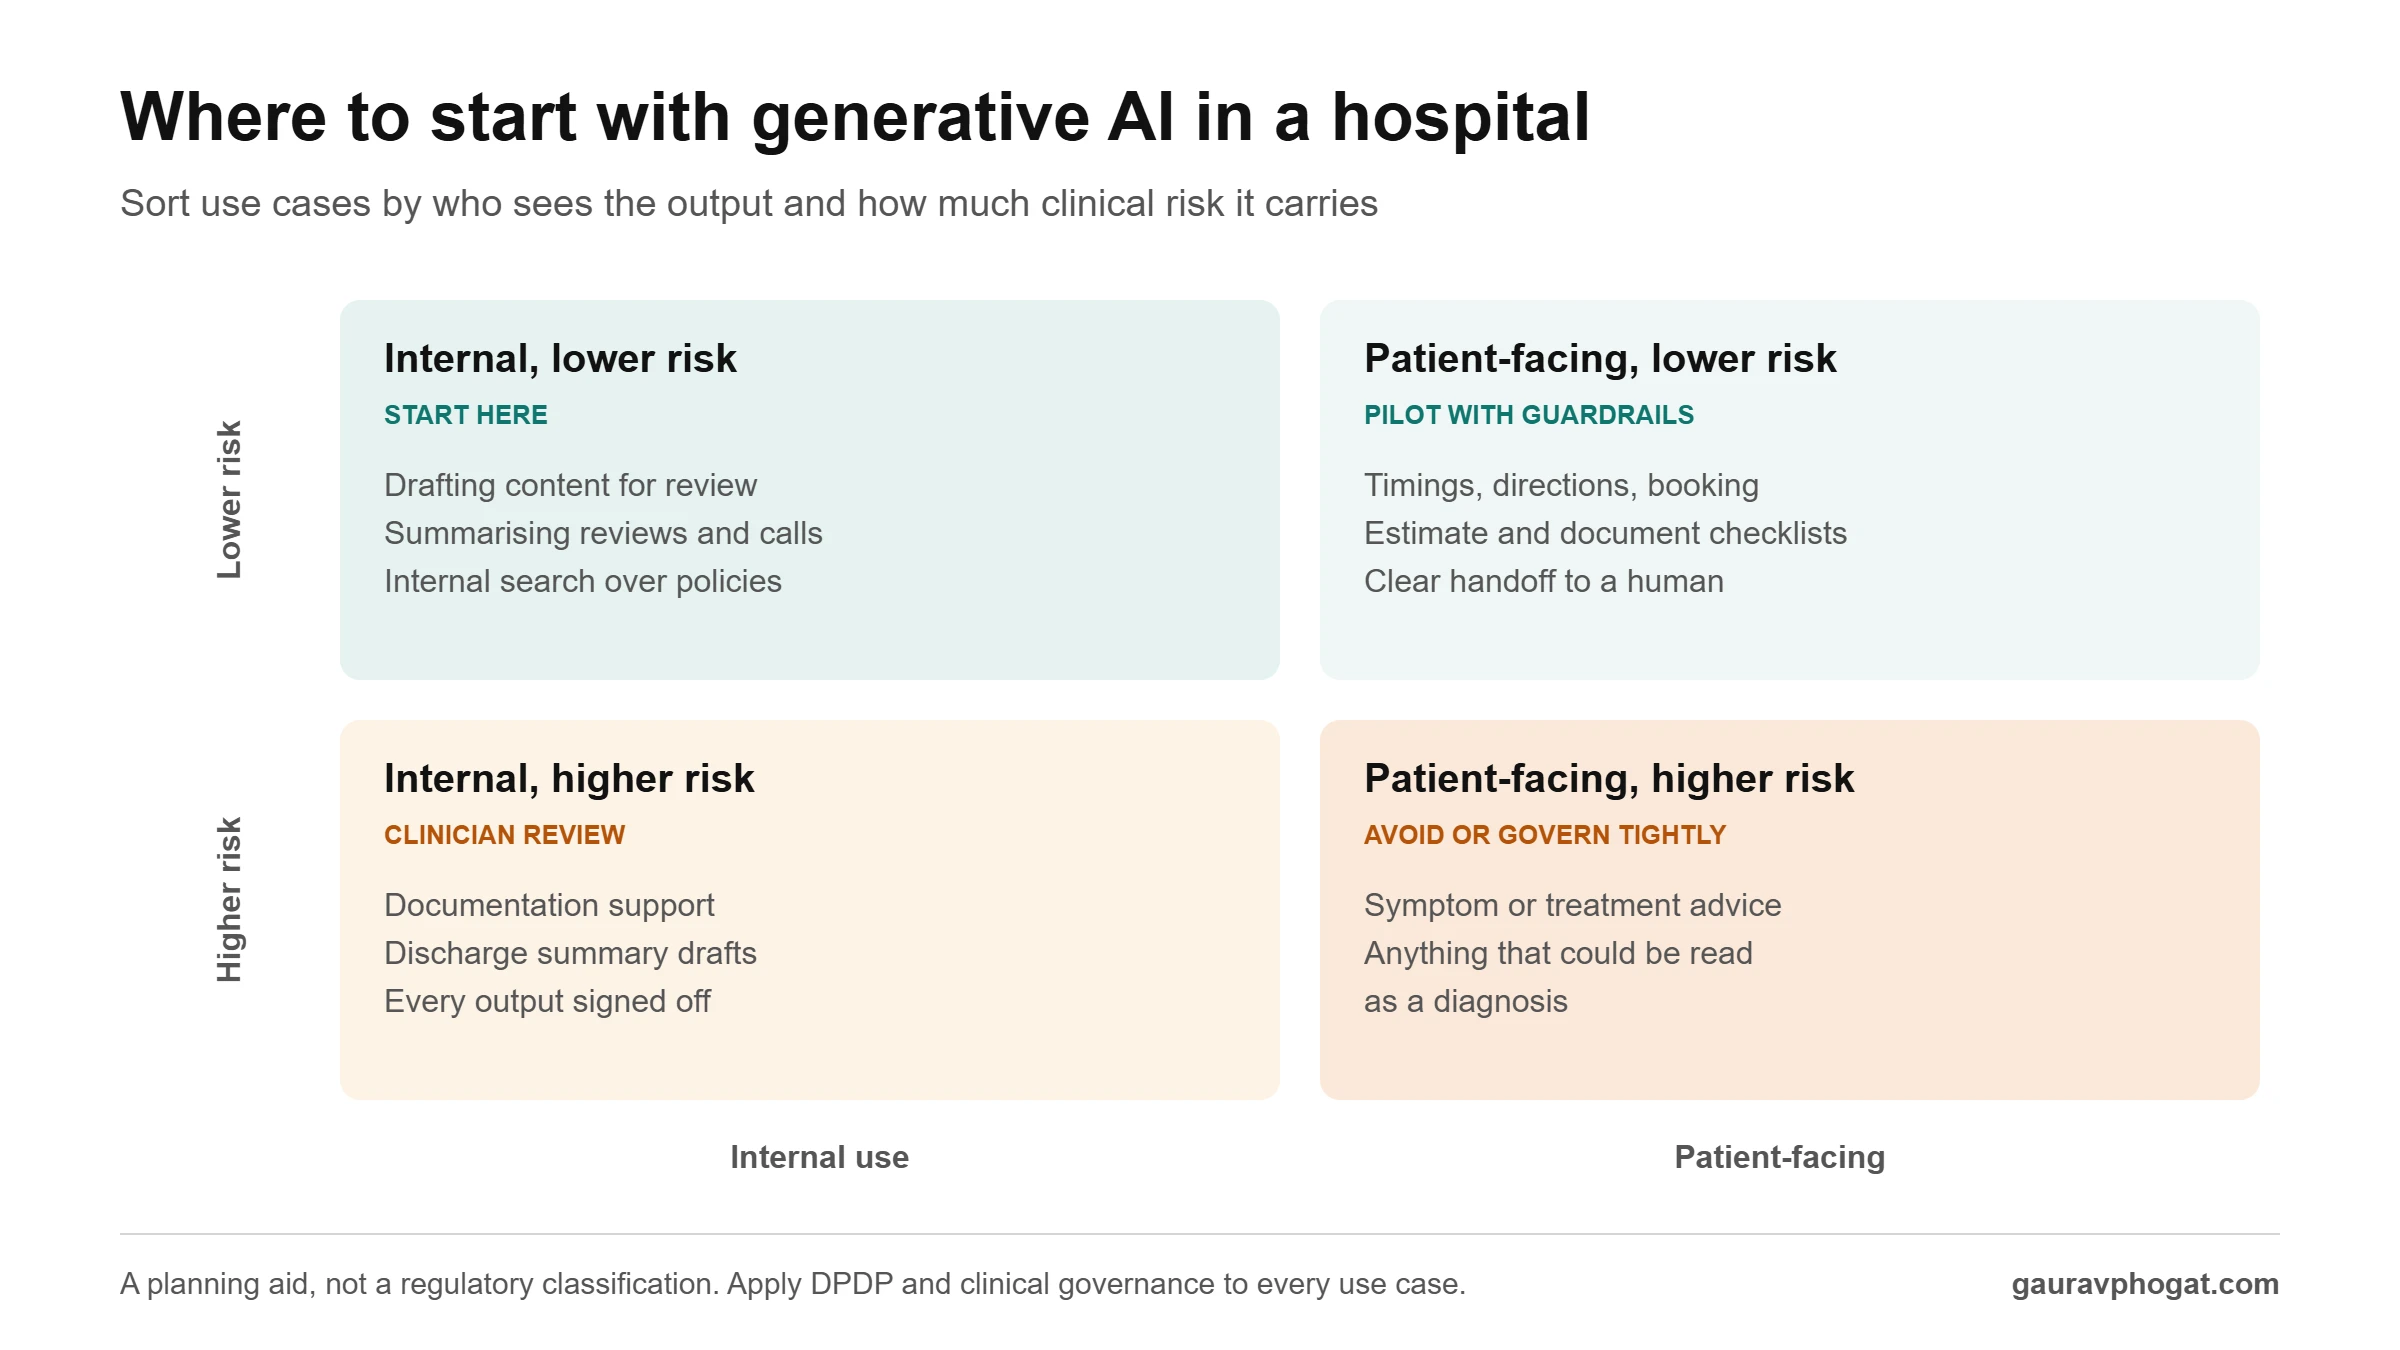
Where generative AI works in Indian hospitals today
1. The patient front door: WhatsApp, chat and enquiries
Indian patients already message hospitals on WhatsApp, at all hours and in several languages. Generative AI can answer the logistical questions (timings, directions, documents, which doctor sees what), collect details and route the enquiry to the right desk. The measure that matters is resolution, not deflection; I set out the difference in chatbot containment vs resolution. For the plumbing, see the WhatsApp Business API for hospitals and WhatsApp as the hospital front door.
The hard rule: the system can route a medical question, it should not answer one. Using AI to triage enquiries without making clinical calls covers where that line sits in practice.
2. The contact centre and voice
Voice bots now handle multilingual calls well enough for appointment booking, report status and reminders. The economics depend on which calls you automate and how cleanly a caller reaches a human. Voice bots and contact-centre cost works through the numbers a CFO will ask for, and when automation should not answer the phone covers the calls to leave alone.
3. Content at scale, with medical accuracy
Generative AI drafts patient education pages, FAQs, video scripts and regional-language versions in minutes. The risk is fluent text that is subtly wrong. The workable model is AI drafting, a named doctor reviewing and a clear record of who approved what. I describe it in AI content at scale without wrecking medical accuracy and where the review line sits for doctor content. A shared prompt library keeps quality consistent across a team. For the full marketing picture, from planning and paid media to chatbots, CRM follow-up and measurement, see my stage-by-stage guide to AI in healthcare marketing.
4. Being found by AI search
Generative AI also changes how patients find you. ChatGPT, Gemini, Perplexity and Google’s AI Overviews now answer many health and hospital questions directly. Hospitals that publish clear, reviewed, well-structured answers get cited; others disappear from the answer. Start with how hospitals get cited by AI search, SEO vs GEO for hospitals and structured data for hospitals.
5. Documentation support
Ambient documentation tools listen to a consultation and draft the note for the doctor to edit and sign. Done well, they give doctors time back and improve records. They also touch patient data and clinical records, so consent, accuracy checks and clinical ownership come first. Ambient documentation in the consultation room covers the questions to settle before a pilot.
6. Internal knowledge and operations
Some of the quietest wins are internal: searching policies and SOPs, summarising long vendor contracts, drafting board notes, answering staff questions about benefits or processes. These carry low patient risk and build the organisation’s confidence before anything faces a patient.
Where it should not go yet
- Diagnosis or treatment advice to patients from a general-purpose model, without a clinician in the loop.
- Unsupervised medical answers on chat, WhatsApp or voice. Route, do not advise.
- Anything that hides the human. Patients should know when they are talking to software and how to reach a person.
- Personal health data in tools you do not control. Check where data goes, who can see it and how long it is kept.
Putting AI in front of patients without an incident and a non-clinical risk framework for AI in hospital operations go deeper on guardrails.
Healthcare chatbots: what they do, their limits and safety
A healthcare chatbot, sometimes called a medical chatbot, is software that talks with patients by text or voice on WhatsApp, a website, an app or the phone. In a hospital it should do four jobs well: answer logistical questions from approved content, complete simple tasks such as booking, collect details for a callback, and hand over to a person quickly. The short definition is in the glossary entry on healthcare chatbots.
What a good healthcare chatbot does
- Answers timings, directions, doctor schedules, documents to bring and published package prices, from content the hospital has approved.
- Books, reschedules and cancels appointments, and shares report status.
- Recognises symptom or emergency language and routes at once to a nurse, a doctor or emergency contact details.
- Says that it is software, and offers a person at every step.
- Logs every conversation and lead into the CRM with its source.
Its limits. General-purpose language models can sound sure and be wrong, still stumble on mixed Hindi and English or regional languages, and cannot examine anyone. Under India’s Telemedicine Practice Guidelines, 2020, platforms based on AI and machine learning are not allowed to counsel patients or prescribe medicines (summary). So the design rule is the one I use on every project: route, do not advise.
Safety checks before go-live
- A list of blocked topics (diagnosis, dosage, treatment choices), tested with real patient messages.
- Emergency signposting tested in every language the bot accepts.
- A named owner who reviews a sample of conversations every week.
- A consent step and privacy notice under the DPDP Act before the bot collects any health details.
- A success measure based on resolution, not containment.
Containment is the trap: a bot that keeps patients away from humans looks efficient until you count how many gave up. I explain the difference in chatbot containment vs resolution. If you are buying one, the healthcare chatbot RFP checklist lists the questions to put to vendors.
The India context
Three things make Indian deployments different. First, language: patients switch between English, Hindi and regional languages, often in one message, so test in the languages your patients actually use. Second, channel: WhatsApp and the phone carry far more of the patient conversation than web forms or apps. Third, regulation: the Digital Personal Data Protection Act, 2023 and the DPDP Rules, 2025 shape consent, notice and retention for any system that handles patient data. Professional conduct rules for doctors and advertising guidelines still apply to anything the AI says in your name. None of this is legal advice; involve your legal and data protection teams early.
Risks and regulation of AI in healthcare in India
India does not have one dedicated law for AI in healthcare. Several existing rules apply, depending on what the system does. This is an operator’s reading, not legal advice; check the specifics with your legal, regulatory and data protection teams.
| Rule | What it covers | What it means in practice |
|---|---|---|
| Digital Personal Data Protection Act, 2023 and DPDP Rules, 2025 | Personal data, including health data: consent, notice, purpose, retention and breach handling | Consent and a clear notice before any AI system collects patient details; know where each vendor stores and processes data. See the DPDP Act entry. |
| ICMR Ethical Guidelines for Application of AI in Biomedical Research and Healthcare (2023) | Ten principles, including autonomy, safety and risk minimisation, data privacy, accountability and liability, non-discrimination and fairness, and validity | Patients should know when AI is involved in decisions about them, someone must be accountable for each system, and tools should be validated on the population they serve. |
| CDSCO guidance on medical device software under the Medical Devices Rules, 2017 | Software that diagnoses, monitors or informs treatment can be a medical device, classed A to D by risk | Check the regulatory status of any diagnostic or clinical decision tool before you deploy it. |
| Telemedicine Practice Guidelines, 2020 | Remote consultations by registered doctors | AI can support a doctor but cannot counsel patients or prescribe; the final advice comes from the doctor. |
| Professional conduct and advertising rules | What doctors and hospitals say in public | Anything a bot or AI-drafted page says in your name follows the same rules: no claims, guarantees or comparisons. |
The risks I watch for
- Confident wrong answers, in chat or in drafted content.
- Bias, when a model was trained on data that does not look like Indian patients.
- Privacy leaks through third-party tools whose data handling you do not control.
- Automation without accountability, where no one owns the output.
- Over-trust, when staff stop checking because the tool is usually right.
My working rule: the closer a system gets to a diagnosis or a treatment decision, the more of these rules apply and the more a clinician must own the output. Putting AI in front of patients without an incident covers the guardrails.
A 90-day way to start
- Weeks 1 to 2: pick one problem with a number attached, such as unanswered WhatsApp enquiries after 8 pm or report-status calls. Write down today’s baseline.
- Weeks 3 to 6: build a narrow pilot with a clear handover to humans, reviewed scripts and a log of every conversation. Get legal and clinical sign-off on scope.
- Weeks 7 to 10: run it on real traffic for a defined segment. Review a sample of conversations every week.
- Weeks 11 to 13: compare against the baseline, decide to scale, fix or stop, and write down why.
Most pilots fail after this point, not during it. Why hospital AI pilots never reach production and the data work nobody budgets for explain why, and an AI strategy a hospital group can execute shows how to sequence the next projects.
How to measure it
Measure what the business already tracks: enquiries answered within a set time, appointments booked from those enquiries, calls handled without a callback, hours of doctor time returned, content published with review completed. Avoid vanity measures such as messages sent or tokens used. Measuring an AI project when nothing clinical is being claimed gives a template.
Where generative AI sits in the patient journey
If you map the journey from first search to follow-up, generative AI fits naturally at the search, enquiry, booking, preparation and follow-up stages, and much less at the clinical core. Where AI belongs in the patient journey maps it stage by stage, and healthcare marketing automation in India shows where rules-based automation is still the better tool.
Sources and further reading
- report (theweek.in)
- summary (medianama.com)
- Ethical Guidelines for Application of AI in Biomedical Research and Healthcare (icmr.gov.in)
- guidance on medical device software (cdsco.gov.in)
Questions people ask
Generative AI uses large language models and similar systems to produce text, speech and summaries. In healthcare it is used for patient conversations, content, documentation support and internal knowledge. It differs from predictive AI, which scores or classifies data such as scans.
Mostly outside the diagnosis: answering and routing WhatsApp and phone enquiries, voice bots for bookings and report status, drafting patient education content for doctor review, improving visibility in AI search, documentation support and internal knowledge search.
Not without a clinician in the loop. A general-purpose model can give fluent but wrong answers. The safer pattern is to let the system answer logistical questions and route medical ones to a doctor or nurse, with emergency signposting.
Conversational AI talks with people through chat or voice. Agentic AI also takes actions on its own, such as checking availability and booking an appointment. Agentic systems need stronger controls because their mistakes become actions, not just words.
The Digital Personal Data Protection Act, 2023 and the DPDP Rules, 2025 govern consent, notice, purpose and retention for personal data. Any AI system handling patient data needs a clear legal basis, a privacy notice and controls on where data goes. Check specifics with your legal team; this is not legal advice.
One with a clear baseline and low clinical risk, such as after-hours WhatsApp enquiries or report-status calls. It shows value quickly and builds confidence before anything more sensitive.
About 90 days is realistic: two weeks to define the problem and baseline, four weeks to build and get sign-off, four weeks of live use, and a few weeks to review and decide.
Use measures the business already tracks: enquiries answered on time, appointments booked, calls resolved without callbacks, doctor hours returned and content published with review complete. Compare against a baseline taken before the pilot.
It can draft it. A named doctor should review and approve every page, and the page should show who reviewed it and when. Content must also follow professional conduct rules and advertising guidelines.
Increasingly well for Hindi and major regional languages, and less evenly for mixed-language messages and smaller languages. Test with real patient messages in the languages your patients use before going live.
Usually not because the model is weak. Common causes are no clear owner, messy or inaccessible data, no budget for integration and change management, and no agreed measure of success.
Rarely. Most hospitals do better configuring proven platforms with their own content, guardrails and integrations, and spending their effort on data, workflow and review rather than model training.
Patients increasingly get answers from AI assistants and AI Overviews. Hospitals that publish clear, reviewed, well-structured answers with good structured data are more likely to be cited in those answers.
AI in healthcare is software that learns from data to recognise patterns, predict, write or talk, used in hospitals, clinics, labs and public health programmes. It splits into clinical uses, such as support for reading scans, and non-clinical uses, such as booking, contact centres, operations and content.
AI reading of chest X-rays in TB screening under the national TB programme, draft clinical notes for doctors to edit and sign, WhatsApp and voice assistants for appointments and report status, bed and roster forecasting, and drafting patient education for doctor review.
Through several existing rules rather than one AI law: the DPDP Act, 2023 and DPDP Rules, 2025 for personal data, ICMR’s 2023 ethical guidelines for AI in biomedical research and healthcare, CDSCO rules for software that works as a medical device, and the Telemedicine Practice Guidelines, 2020, which do not allow AI platforms to counsel patients or prescribe. Check specifics with your legal advisers.
Read my takes first in Google Search
