

Patient acquisition strategy for hospitals: a full-funnel guide for India
Reviewed on by Gaurav Phogat. Statistics checked against their original sources on the same date.
A good patient acquisition strategy for a hospital starts with capacity, not channels. Grow specialties that can take more patients, capture demand in search and referral networks, convert enquiries fast on calls and WhatsApp, follow up through a CRM, and judge every rupee on cost per treated patient.
Updated 11 October 2026 as per the NMC’s new advertising guidelines. Under the NMC’s Guidelines on Ethical Advertising and Public Communication, in force since 6 October 2026, doctors and hospitals can no longer request or share patient reviews or testimonials for promotion, use before-and-after photos or promotional patient stories (even with consent), offer discounts or other inducements, or make superiority or guaranteed-outcome claims. The advice below has been revised accordingly. See what the 2026 NMC guidelines allow.
Last updated: 1 October 2026.
Most patient acquisition advice online is written for US clinics: email newsletters, online scheduling and patient portals. Indian hospitals face a different funnel. Patients ask family and their local doctor, search for the doctor’s name, call the hospital, and often message on WhatsApp before they decide. Insurance, cashless approval and distance matter as much as reputation. This playbook is built for that reality.







Start with capacity: what can you actually serve?
Start patient acquisition by agreeing three lists with unit heads: grow, for specialties with spare OPD slots, beds or theatre time; hold, for specialties near capacity where marketing should protect reputation rather than add volume; and build, for new services, doctors or units that need demand created. This makes acquisition a hospital decision.
Acquisition fails when marketing pushes demand into a department that cannot absorb it. Before you plan channels, sit with unit heads and agree three lists.
- Grow: specialties with OPD slots, beds or theatre time to spare and doctors who want volume.
- Hold: specialties running near capacity, where marketing should protect reputation rather than add volume.
- Build: new services, new doctors or new units that need demand created before they open. My hospital launch marketing plan covers this case.
This turns acquisition from a marketing project into a hospital decision, and it gives you the right to say no to campaigns that will only produce complaints.
Patient acquisition strategy for hospitals: the full-funnel playbook
 2:54
A good patient acquisition strategy does not start with channels. It starts with capacity. Then it captures demand where patients search and ask, converts it on the phone and WhatsApp, and is judged on cost per treated patient. This version is updated for the NMC's advertising guidelines of October 2026.
Read the transcript
A good patient acquisition strategy does not start with channels. It starts with capacity. Then it captures demand where patients search and ask, converts it on the phone and WhatsApp, and is judged on cost per treated patient. This version is updated for the NMC's advertising guidelines of October 2026.
Acquisition fails when marketing pushes demand into a department that cannot absorb it. So sit with unit heads and agree three lists. Grow. Specialties with slots, beds or theatre time to spare, and doctors who want volume. Hold. Specialties near capacity, where marketing should protect reputation rather than add volume. Build. New services, doctors or units that need demand created before they open.
An illustrative example. A cardiology department asks for more patients, but its OPD is full until two in the afternoon every day. More ads would only lengthen waiting times and generate complaints. The better move is to market the afternoon and evening clinics.
Now the channels. Local and organic search: Business Profiles per unit, doctor pages and answer-first content. It also feeds AI answers. Paid search, run by specialty and unit, to buy intent you can serve now. Referral doctors, corporates and insurers, which bring volume that never shows up in web analytics. And WhatsApp and the phone, where most enquiries are actually closed.
The biggest gains rarely come from a new channel. They come from answering faster and following up properly. Measure time to answer calls, return missed calls and reply on WhatsApp, and report it next to cost per lead. Route calls, messages, forms and walk-ins into one CRM record per patient. And give agents scripts that route to the right doctor and offer a specific slot.
A returning patient, a second procedure or a family member's care costs far less to acquire than a new patient. Recall reminders and post-discharge calls belong in the plan, with clear consent for each use of the data. Review requests do not, under the NMC's guidelines of October 2026.
Four mistakes to avoid. Running campaigns for specialties that have no slots. Sending paid traffic to the homepage. Judging agencies on leads and cost per lead. And using patient data for marketing without clear consent under the DPDP Act.
The full guide, with sources and checklists, is on gauravphogat.com. The link is in the description.
What are the stages of the hospital patient acquisition funnel?
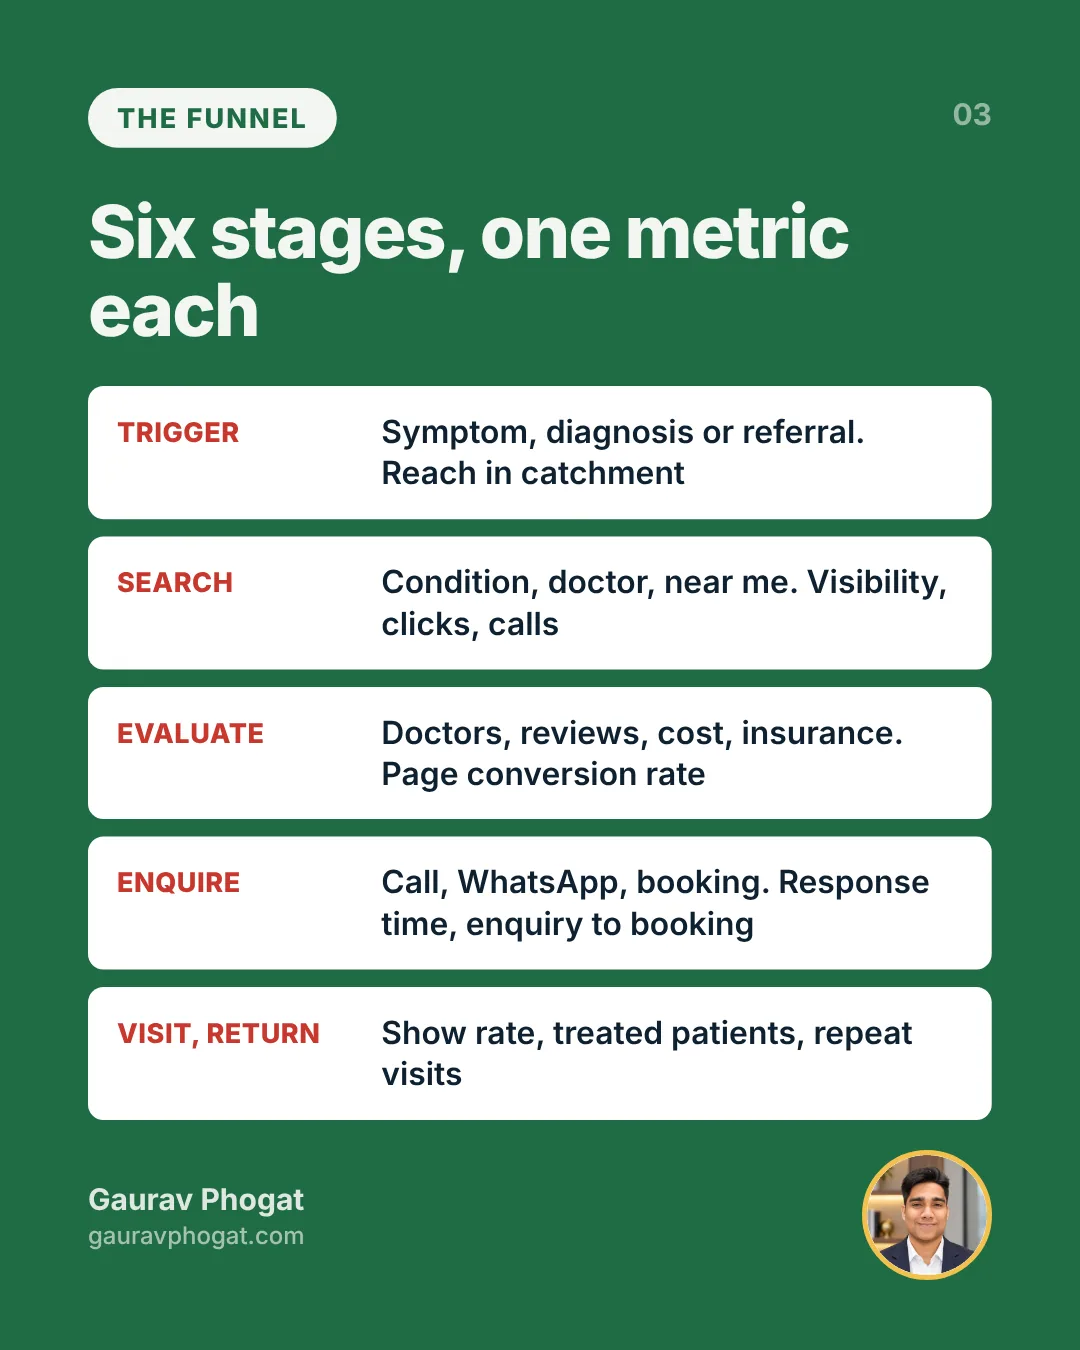
The hospital patient acquisition funnel has six stages: trigger, when a symptom, diagnosis or referral starts the search; search; evaluate, comparing doctors, reviews and cost; enquire; visit; and treat and return. Every channel and metric should map to one stage, so losses are visible and each channel is judged on the stage it serves.
I use six stages. Every channel and every metric maps to one of them.
These stages follow the patient. For the hospital’s side of the same journey, from capacity through to proving cost per treated patient, I use the six-stage healthcare marketing framework.
| Stage | What the patient does | What the hospital must do | Metric |
|---|---|---|---|
| Trigger | Notices a symptom, gets a diagnosis or a referral | Be present in health content, camps, screening and referral networks | Reach in target catchment |
| Search | Searches the condition, doctor or “near me” | Rank in local, organic and AI search, run paid search where capacity exists | Visibility, clicks, calls |
| Evaluate | Compares doctors, reviews, cost and insurance | Strong doctor pages, reviews answered, clear cost and cashless information | Page conversion rate |
| Enquire | Calls, messages on WhatsApp or books online | Answer in minutes, triage correctly, log in CRM | Response time, enquiry to booking rate |
| Visit | Attends OPD or diagnostics | Confirm and remind, smooth arrival and billing | Show rate |
| Treat and return | Has a procedure or ongoing care, refers others | Follow-up, recall and private feedback | Treated patients, repeat visits, reviews |
My longer piece on the multi-unit patient acquisition funnel explains how this works when a group has many hospitals in one city.
An illustrative example: a cardiology department asks marketing for more patients, but its OPD slots are full until 2 pm every day. Pushing more ads would only lengthen waiting times and generate complaints. The better move is to market the afternoon and evening clinics, and to put spend behind a newer specialty that has doctors waiting for volume.
Which channels bring patients to Indian hospitals?
Six channel groups bring patients to Indian hospitals: local and organic search, including AI answers; paid search by specialty and unit; doctor reputation through profiles, video and reviews; referral doctors and partners; corporate, insurance and community programmes; and international patients. Each needs its own owner, landing pages and outcome metric rather than one shared lead target.
1. Local and organic search
Google Business Profiles per unit, specialty and doctor pages, and answer-first content capture most free, high-intent demand. Local search also feeds AI Overviews and assistants, which increasingly answer “which hospital for” questions. See local SEO for hospitals in India and my channel guide to hospital digital marketing in India.
2. Paid search
Google Search Ads buy intent you can serve now. Run them by specialty and unit, send traffic to specific landing pages, and optimise on booked and treated patients through offline conversion import, not on form fills. My Google Ads guide for doctors and hospitals goes deeper.
3. Doctor reputation
Patients choose doctors. Factual doctor profiles, doctor-led educational video and steady patient reviews raise conversion across every other channel. The NMC code limits promotional claims, so keep this educational and factual. See hospital brand vs doctor brand.
4. Referral doctors and partners
General practitioners, smaller nursing homes and diagnostic centres send a large share of planned procedures in many Indian cities. Treat referral relationships as a channel with its own CRM tracking, so you know which partners send patients and how those patients are looked after.
5. Corporate, insurance and community
Corporate health check contracts, insurer and TPA networks, and community health camps create planned volume and long-term relationships. They need a clear offer, a booking path and follow-up for abnormal results.
6. International patients
For hospitals serving medical travellers, acquisition runs through facilitators, embassies and digital channels in source countries, each with different expectations. My international patient funnel piece covers this.
Conversion is where most acquisition budgets leak
Most acquisition budgets leak after the enquiry, not before it. The biggest gains come from faster responses to calls and messages, one CRM record per patient across calls, WhatsApp, forms and walk-ins, triage scripts that route patients to the right doctor and explain costs, and follow-up rules for people who enquire but do not book.
In my experience the biggest gains rarely come from a new channel. They come from answering faster and following up properly.
- Response time. Measure time to answer calls, time to return missed calls and time to reply on WhatsApp. Report it next to cost per lead.
- One record per patient. Route calls, WhatsApp, web forms and walk-ins into one CRM record so follow-up is not duplicated or lost. My hospital CRM implementation plan shows how.
- Triage scripts. Agents should route patients to the right specialty and doctor, explain cost and insurance clearly, and never give medical advice.
- Follow-up rules. Patients who enquire but do not book should get a call-back and a reminder within a defined window, with consent.
I cover the automation side in healthcare marketing automation in India and the follow-up after a visit in automating patient follow-up after OPD.
Retention and recall are acquisition too
A patient returning for follow-up, a second procedure or a family member’s care costs far less than a new patient. Recall reminders, post-discharge calls, feedback requests and review prompts therefore belong inside the acquisition plan, each with clear consent for how patient data is used under India’s data protection rules.
A patient who returns for follow-up, a second procedure or a family member’s care costs far less to acquire than a new one. Recall reminders, post-discharge calls, feedback requests and review prompts belong in the acquisition plan, with clear consent for each use of the data.
Why measure cost per treated patient instead of cost per lead?
Cost per lead rewards cheap, low-quality enquiries, while cost per treated patient, measured by specialty and unit, rewards channels that bring patients who actually receive care. Calculating it requires the CRM to be linked to appointment and billing status, so every enquiry can be followed through to a treated outcome.
Cost per lead rewards cheap, low-quality enquiries. Cost per treated patient, by specialty and unit, rewards channels that bring patients who actually get treated. To calculate it you need the CRM linked to appointment and billing status. I explain the method in cost per treated patient.
| Metric | Why it matters | Watch out for |
|---|---|---|
| Cost per treated patient | Ties spend to real outcomes | Needs CRM and billing integration |
| Enquiry to appointment rate | Shows contact centre quality | Low rates often mean slow response |
| Show rate | Shows reminder and access quality | Varies by specialty and distance |
| Share of treated patients by channel | Shows channel mix health | Referral and walk-in tagging is often missing |
| Repeat and referred patients | Shows experience and retention | Needs consistent patient identity |
Patient acquisition for a multi-unit group
Hospital groups face two extra problems: units competing for the same patient and central campaigns that ignore local capacity. Solve both with a shared CRM data model, clear rules for which unit receives each enquiry, central paid media with unit-level budgets, and a weekly view of capacity by specialty across all units.
Groups face two extra problems: units competing for the same patient, and central campaigns that ignore local capacity. Solve both with a shared data model in the CRM, rules for which unit receives an enquiry, central paid media with unit-level budgets, and a weekly view of capacity by specialty. My notes on centralising marketing across hospital units cover the governance.
What patient acquisition mistakes should hospitals avoid?
Common acquisition mistakes include running campaigns for specialties with no slots, sending paid traffic to the homepage, judging agencies on leads and cost per lead, letting each unit run separate phone numbers and WhatsApp accounts, using patient data without clear DPDP consent, and ignoring referral doctors because they never appear in digital dashboards.
- Running campaigns for specialties that have no slots.
- Sending paid traffic to the homepage.
- Judging agencies on leads and cost per lead.
- Letting each unit run its own phone numbers and WhatsApp accounts with no shared record.
- Using patient data for marketing without clear consent under DPDP.
- Ignoring referral doctors because they do not show up in digital dashboards.
A 90-day patient acquisition plan
In month one, agree the grow, hold and build specialties and audit tracking, Google profiles and response times. In month two, rebuild landing pages for the grow list, restructure paid search and connect calls to the CRM. In month three, report cost per treated patient and shift budget toward channels that produce treated patients.
- Month 1: agree grow, hold and build specialties; audit tracking, Google profiles, response times and consent; fix the biggest leaks.
- Month 2: rebuild landing pages for the grow list, restructure paid search, connect calls and WhatsApp to the CRM, start referral tracking.
- Month 3: report cost per treated patient for the first time, shift budget toward the channels that prove out, and launch recall for existing patients.
Related: Policybazaar is building hospitals. It already owns the patient’s wallet.
Key statistics, with sources
Indian patient behaviour explains why acquisition must cover the whole funnel. Most patients rely on personal recommendations when choosing a hospital, most also look for objective information that few can find, and almost all want a single point of contact. Trust, clear information and coordinated follow-up together decide where patients finally go.
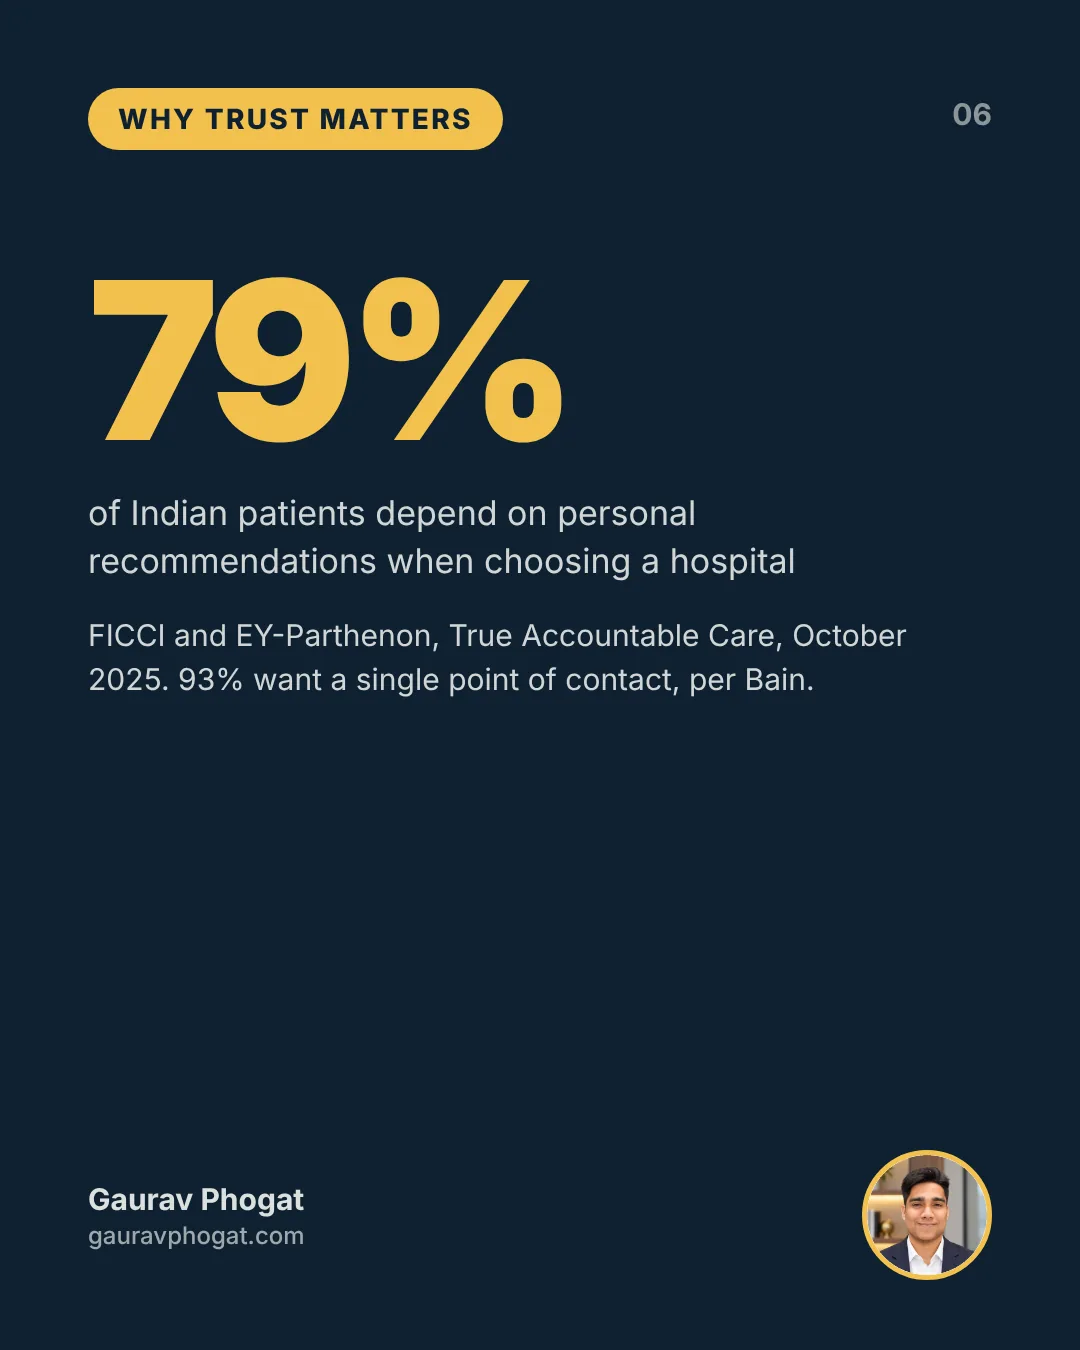
- 79% of Indian patients depend on personal recommendations when choosing a hospital, according to FICCI and EY-Parthenon. Source: FICCI and EY-Parthenon, True Accountable Care, October 2025.
- 83% of Indian patients actively look for objective, accessible information to guide their healthcare choices, but only about a third can easily find objective clinical outcome information, according to FICCI and EY-Parthenon. Source: FICCI and EY-Parthenon, True Accountable Care, October 2025.
- 93% of Indian healthcare consumers want a single point of contact to manage their healthcare journey, and 42% report long waiting times at facilities, according to Bain & Company. Source: Bain & Company, 2026 Asia-Pacific Front Line of Healthcare, reported by ANI, June 2026.
Sources and further reading
- Google Ads: About offline conversion imports: how to send booked and treated outcomes back to Google Ads.
- WhatsApp Business Messaging Policy: the opt-in businesses need before messaging people.
- Google: Guidelines for representing your business on Google: the rules for one accurate profile per real location.
Questions people ask
Start with specialties that have capacity, capture demand in local, organic, AI and paid search plus referral networks, convert enquiries fast on calls and WhatsApp, follow up through a CRM, and measure cost per treated patient.
It is the set of activities that bring new patients to a hospital or clinic, from awareness and search through enquiry, appointment and treatment.
Local search, doctor reputation and referral doctors usually drive the largest share, with paid search adding intent for specific specialties. The mix varies by city, specialty and hospital size.
Divide the spend on a channel by the number of patients from that channel who were treated in the period. It needs the CRM linked to appointment and billing records.
Cheap leads are often duplicates, wrong specialty or never answered. Cost per lead rewards volume, while cost per treated patient rewards channels that bring patients who get care.
As quickly as possible, ideally within minutes for calls and WhatsApp. Slow response is one of the most common reasons good campaigns produce few appointments.
Strengthen doctor pages and Google profiles, run specialty-specific paid search where slots exist, answer enquiries fast, remind booked patients, and build referral and corporate relationships.
In many Indian cities referral doctors drive planned procedures. Tracking them as a channel in the CRM shows which relationships matter and how referred patients are looked after.
It joins every enquiry into one patient record, routes it to the right team, triggers follow-ups and links marketing to appointments and treatment so spend can be judged on outcomes.
Groups need rules on which unit receives an enquiry, shared data and CRM, central media with unit budgets, and a view of capacity by specialty so campaigns do not overload one unit.
Yes. Lead forms, call recordings, WhatsApp and remarketing need clear notice and consent, and patient data cannot be reused for marketing without consent.
Fixes to response time and landing pages show results within weeks. Local SEO, doctor reputation, content and referral programmes build over several months.
No. Focus spend on specialties with capacity and doctors who want volume, protect reputation where you are full, and build demand early for new services.
Read my takes first in Google Search
