
Famous leaders in healthcare and what they teach leaders today
The most useful famous leaders in healthcare are historical figures — Nightingale, Snow, Semmelweis, Lister, Seacole, Barton, Saunders, Anandibai Joshi, Kadambini Ganguly and Dr Bidhan Chandra Roy — whose problems still look like a modern hospital leader’s. Each is read through an operator’s lens: shaping evidence, winning adoption, designing around the patient and building institutions that outlast their founders.
Most lists of famous leaders in healthcare are either a roll-call of current chief executives or a history lesson with no point attached. I wanted something more useful: the handful of historical figures whose problems look uncannily like the ones a modern hospital leader faces on a Tuesday afternoon — how to get a decision-maker to act on evidence, how to change a practice professionals are attached to, how to build something that survives its founder, how to make care feel like care to the person receiving it.
None of them ran a digital team, a contact centre or a CRM. All of them ran into the same walls. The data was there and nobody acted on it. The right answer arrived and the room rejected it. The system was not designed around the patient, and someone had to go around it.
What follows is who each of them was, in a sentence or two, and the lesson I think a healthcare operator — commercial, digital, brand or general management — can actually use. Their failures are often more instructive than their monuments.
Why this list of famous leaders in healthcare is historical
Every figure here is from history, and that is deliberate. The lessons are settled: we know how their stories ended, which ideas stuck and which efforts collapsed. Nobody is ranking living peers, nobody is campaigning for a place, and nobody’s reputation this year depends on how they are described.
I have kept to facts that are widely established and left out anything contested, because a lesson built on a disputed anecdote is not worth much. And I have grouped them by the problem they solved rather than by era, because that is how you will use them.
The leaders who won with evidence
Florence Nightingale
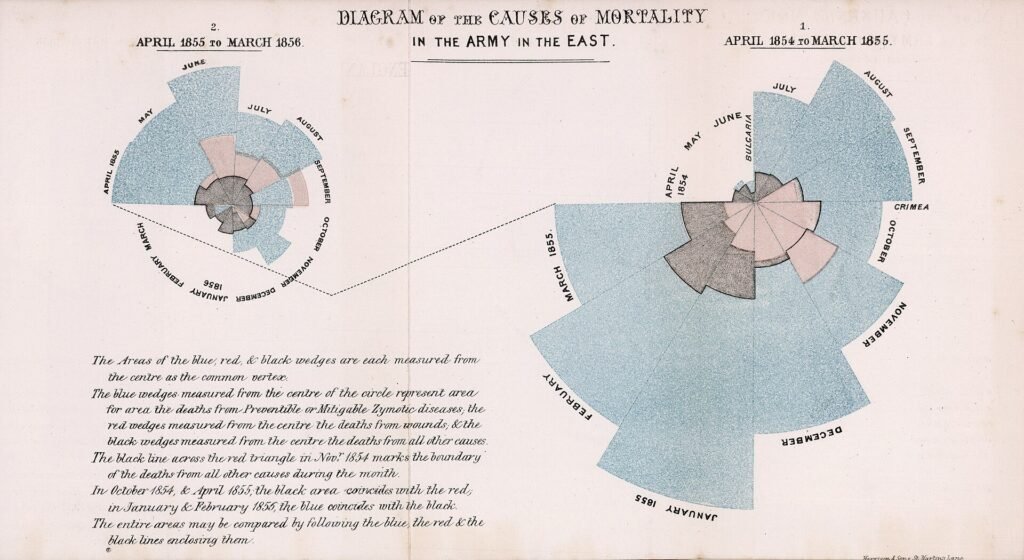
Nightingale is remembered as the nurse with the lamp in the Crimean War. She deserves to be remembered as one of the earliest people to use a chart to change government policy. She collected mortality data from military hospitals, showed that far more soldiers were dying of preventable disease than of their wounds, and presented it in diagrams designed for officials who would never read a statistical table.
The lesson is not “use data”. Everyone says that. It is that she designed the evidence for the specific person who had to decide, and made the pattern impossible to miss in one glance. Most board packs I have seen do the opposite — they present everything, in the format the analyst finds convenient, and leave the decision-maker to find the point. If your chart needs a presenter to explain it, it will not survive being forwarded.
John Snow
Snow was a London physician who, during a cholera outbreak, marked the homes of the dead on a street map and found them clustered around a single public water pump. He persuaded the local authorities to remove the pump’s handle, at a time when the prevailing theory said cholera spread through bad air.
What I take from Snow is the difference between evidence and a decision. His map was compelling, but what mattered was the narrow action he asked for: take the handle off this pump. He did not ask the authorities to accept a new theory of disease. He asked them to do one cheap, reversible thing. When I have built a case for the executive committee, the requests that got approved were almost always Snow-shaped — one change, one place, a small cost, and a way to see within weeks whether it worked. The ones that stalled asked the room to agree with a worldview first.
The leaders who were right and still lost the room
Ignaz Semmelweis
Semmelweis was a physician at a maternity hospital in Vienna who noticed that the ward staffed by doctors and medical students had far higher maternal deaths than the ward run by midwives. He concluded that doctors were carrying contamination from autopsies to patients, introduced handwashing with a chlorine solution, and saw deaths fall sharply. His colleagues largely rejected him, and he died before the germ theory that explained his findings was accepted.
This is the most important story on the list for anyone trying to change how a hospital works. Semmelweis had the right answer and the evidence. He lost anyway. He was slow to publish, he framed his findings as an accusation, and he treated disagreement as a moral failing. The profession closed ranks, as any profession would.
Change management in a clinical organisation is not about being right. It is about making it possible for people to change without first admitting they were wrong. Every time I have pushed a new process into a hospital — an enquiry-handling workflow, a new way of presenting doctor profiles, an approval path for content — the version that worked gave clinicians a way to own the improvement. The version that failed made them defend the past. That is most of what I mean by clinician buy-in, and Semmelweis is the cautionary tale I would put in front of every new hire who arrives certain they know better.
Joseph Lister
Lister was a British surgeon who applied the emerging germ theory to surgery, using carbolic acid to clean wounds, instruments and dressings. His methods were resisted for years before they became standard.
Where Semmelweis failed, Lister persisted in the right way. He published, demonstrated his methods to anyone who would watch, trained people who carried the practice into other hospitals, and kept refining the technique rather than defending the first version. Adoption came through followers, not argument.
That is how new practice spreads inside a hospital group today. A new tool or workflow does not scale because the central team announces it. It scales because one unit adopts it, a respected unit head vouches for it, and the next unit asks for it. I have learned to spend less time on the launch and more on the second and third adopters.
The leaders who went where the system would not
Mary Seacole
Seacole was a Jamaican-born nurse and businesswoman who offered to serve in the Crimean War and, when official channels did not take her up, travelled there at her own expense. She set up a place near the front where soldiers could get care, food and comfort.
The lesson is uncomfortable for anyone inside a large organisation. Seacole did not wait for the system to design a service around the people who needed it. She went where the patients were. Most gaps in a patient’s experience sit between departments — the enquiry nobody owns, the family member nobody updates, the discharge that ends in confusion. Someone has to step outside the org chart and serve the patient where the structure does not, then use what they learned to redesign the structure so the gap closes for good.
Clara Barton
Barton cared for wounded soldiers in the American Civil War and went on to found the American Red Cross, which she led for many years. The organisation outlasted her by a very long way.
Barton’s lesson is the difference between a mission and an institution. Founders carry an organisation on energy, relationships and personal reputation. Institutions need governance, succession and processes that work when the founder is not in the room — and the move from one to the other is usually painful, including for Barton herself. If a team or platform I built only works because I am there, I have not built anything. The test is whether it runs well a year after I have moved on.
The leader who redesigned care around the patient
Cicely Saunders
Saunders trained as a nurse, worked as a medical social worker, and later qualified as a doctor. She founded the modern hospice movement, built on the idea that people at the end of life needed their pain — physical, emotional, social and spiritual — treated as a whole, with care organised around the person rather than the disease.
The clinical side of her work is not my territory. The design principle is. She started from what the patient and family actually experienced and rebuilt the service backwards from there. Most hospitals still design the journey from the inside out: departments, systems, billing, and the patient fits wherever the handoffs allow. Design from the family’s first anxious phone call onwards and you find failures no departmental dashboard will show. It is also the only honest way to answer what patient experience is worth — you cannot value an experience you have never mapped from the patient’s side.
The Indian pioneers every healthcare leader should know
Any serious list of famous leaders in healthcare for an Indian reader has to include people who built the path here.
Anandibai Joshi
Anandibai Joshi, from Maharashtra, was among the first Indian women to qualify in Western medicine. She travelled to the United States to study, graduated, and returned to India, but died young shortly afterwards, before she could practise for long.
Kadambini Ganguly
Kadambini Ganguly was one of the first women to graduate from an Indian university and among the first Indian women to practise Western medicine. She faced open public hostility for it, trained further abroad, and practised for many years.
What these two teach is not a technique. It is a reminder of what breaking a barrier costs. Both did it against social criticism and institutions that were not built for them. When I look at healthcare leadership in India today, I still see how few women sit in the commercial, digital and general-management seats compared with how many do the work below them. Joshi and Ganguly are a standing question to anyone who hires: who is your system not built for?
Dr B. C. Roy
Dr Bidhan Chandra Roy was a physician who became one of India’s most significant public leaders, including as Chief Minister of West Bengal. National Doctors’ Day in India is observed on 1 July, the anniversary of both his birth and his death.
Roy’s lesson is that clinical credibility and institutional leadership can live in the same person, and that the combination builds trust no amount of marketing can buy. Most healthcare organisations separate the two: doctors carry trust, managers carry the organisation. The groups that do well connect them — clinicians in visible leadership, managers who earn clinicians’ respect, a brand that stands on both. An operator can design for that connection even without being the doctor in the room.
What today’s top healthcare leaders in India have in common
I will not name anyone. But the leaders I have worked with or watched from close quarters who actually move organisations share a handful of traits that map onto the figures above.
- They turn data into a decision, not a report. They shape evidence for the person who has to act.
- They ask for small, specific changes. One pump handle before anyone’s worldview.
- They let others own the win. Being right is not the same as being followed.
- They build followers before scale. The second and third adopters get their time.
- They start from the patient’s side of the counter. They map the journey as the family lives it.
- They build institutions, not dependencies. They measure themselves by what still works after they leave.
- They break messy problems into parts. Test one change, keep what works — an engineering mindset applied to people as much as systems.
The order of operations for the next quarter
The leadership lessons only matter if you use them. If I were starting in the next ninety days, this is the order I would go in.
- Redesign one committee chart the Nightingale way. Pick the metric you most need a decision on and rebuild the slide so the point is visible without a presenter.
- Turn your biggest pending proposal into a Snow-shaped request. One change, one unit, a small cost, a signal you can read within weeks — tied to the numbers a board asks for so the result lands in language the board already uses.
- Audit a live change for Semmelweis risk. Does it let clinicians and unit heads own the improvement, or does it ask them to admit they were wrong? Reframe before you escalate.
- Find your second adopter. For whatever you have piloted, identify the next unit head who would vouch for it and spend your time there.
- Map one patient journey from the family’s side. From first enquiry to after discharge, list every handoff where nobody owns the patient. That is your Seacole list.
- Run the Barton test on your own team. Ask what would break if you were away for a month. Fix the top two.
- Look at who your system is not built for — in hiring, promotion, and who gets to present to the board.
The people on this list did not have better tools than you. They had a clearer sense of who needed to decide, who needed to change, and who the whole thing was for.
Questions people ask
Famous leaders in healthcare are the people whose work changed how care is organised, delivered or trusted, not just how it is practised clinically. The list here is deliberately historical — Nightingale, Snow, Semmelweis, Lister, Seacole, Barton, Saunders, Anandibai Joshi, Kadambini Ganguly and Dr B. C. Roy — because their stories have ended and the lessons are settled. Each one maps to a problem a modern operator still faces: evidence, persuasion, adoption, patient experience or institution-building.
The names that recur in almost every account are Florence Nightingale, John Snow, Ignaz Semmelweis and Joseph Lister, alongside Mary Seacole, Clara Barton and Cicely Saunders. For an Indian reader, Anandibai Joshi, Kadambini Ganguly and Dr B. C. Roy belong on the same list. I have chosen them less for fame than for the leadership problem each one solved, or failed to solve, because that is what makes them useful to someone running a hospital function today.
Because the lessons from historical figures are settled and nobody is ranking living peers. We know which ideas stuck and which efforts collapsed, so the lesson is not a matter of opinion or reputation management. A list of current executives tells you who is prominent this year. A list tested by time tells you what actually worked, which is more useful when you are deciding how to run a change programme or a board conversation.
In my experience they turn data into a decision rather than a report, ask for small and specific changes, let others own the win, and build followers before they chase scale. They start from the patient’s side of the counter, build institutions rather than dependencies on themselves, and break messy problems into testable parts. None of these traits is rare in theory. Each is rare in practice because it costs time, credit or control.
Design the evidence for the person who has to decide. Nightingale collected mortality data and presented it in diagrams officials could grasp in one glance, which is why it changed policy. A unit head or CEO can apply this directly to board and committee packs: pick the decision you need, cut everything that does not serve it, and make sure the chart makes its point without a presenter. If it needs explaining, it will not survive being forwarded.
He had the evidence that handwashing cut maternal deaths, but he was slow to publish, framed his findings as an accusation and treated disagreement as a moral failing. His colleagues closed ranks. For anyone driving change in a hospital, the lesson is that being right is not enough. Change sticks when clinicians and unit heads can own the improvement without first admitting they were wrong. Reframe the change before you escalate it.
That clinical credibility is the scarcest asset in any change programme, and that the leaders who used it well — Lister, Dr B. C. Roy — built followers rather than winning arguments. A medical director is often the person who decides whether a new workflow feels like an improvement doctors own or an imposition they defend against. Being involved early, and visibly, is usually worth more than any amount of central communication from management.
Ask for Snow-shaped proposals. Snow did not ask the authorities to accept a new theory; he asked them to remove one pump handle. A CFO reviewing a digital or growth case should push for the same shape: one specific change, one unit, a small and bounded cost, and a signal readable within weeks. Proposals that ask the committee to buy into a worldview first are harder to evaluate and far more likely to drift.
The problems are recognisably the same — persuading decision-makers, changing entrenched practice, serving patients the system misses — but the Indian context adds multi-unit groups, regional languages, mixed payer channels and a very trust-driven patient choice. Joshi, Ganguly and Roy add something the Western list lacks: the cost of breaking barriers in a society not built for you, and the power of combining clinical credibility with public leadership.
You can start within a quarter. Redesigning one committee chart, reshaping one proposal, auditing one live change and mapping one patient journey are all ninety-day pieces of work. Building followers the Lister way and making a team run without you, as Barton’s story demands, takes longer — usually a year or more — because it depends on people changing habits rather than on a document changing.
Treating it as a launch rather than an adoption. The central team announces a new tool or process, expects compliance, and is surprised when units quietly ignore it. What works is Lister’s approach: one unit adopts it, a respected unit head or consultant vouches for it, and the next unit asks for it. Spend less on the launch and more of your time on the second and third adopters.
Look for evidence of the traits rather than the titles. Has the candidate turned data into a decision someone acted on? Have they changed a practice without humiliating the people who held it? Did what they built survive their departure? Joshi and Ganguly also raise a direct question for HR: who is the current hiring system not built for, and how few women reach commercial, digital and general-management seats?
Yes, and often more easily than a large group. A single hospital has fewer layers between the evidence and the decision, so a Snow-shaped proposal can move in weeks. Mapping the patient journey from the family’s side is also more manageable at one site. The Barton test matters just as much: if the unit’s marketing or patient experience only works because one person is there, it has not been built yet.
