

International patient enquiries: how to reply, WhatsApp first
Last reviewed
The first reply to an international patient enquiry, on WhatsApp, email or a web form, decides which hospitals a family shortlists. WhatsApp for international patients carries the entire relationship across a border, not a quick booking. Run it on one verified business number rather than personal phones, roster to your largest markets’ time zones, build approved templates in each supported language, move every report into the CRM the same day, and treat handover between coordinators as the point where cases are actually lost.
Updated 29 October 2026: merged in our guide on the first reply to an international enquiry and added what every reply must carry, what it must never do, replying across channels and how to measure it.









At a glance
| What it carries | The whole cross-border relationship, not a quick booking |
| Set-up | One verified business number, never personal phones |
| Staffing | Rostered to the time zones of your largest markets |
| Content | Approved templates in each supported language |
| Weak point | Handover between coordinators; reports go into the CRM the same day |
Ask any international desk in India where their enquiries actually live and the answer is the same. Not the web form. Not email. A messaging thread, usually on a phone, usually running from the moment a family first hears the hospital’s name until months after the patient has flown home.
WhatsApp for international patients is not the same product as WhatsApp for your domestic front door, even though it is the same app. At home the channel is mostly about speed and convenience: book me, remind me, send me the report. Across a border it is carrying the entire relationship. It is where the family sends photographs of reports they cannot post, where an estimate is discussed, where a coordinator proves a human being exists, where the son in another country joins the conversation, and where the hospital either earns the trip or loses it.
I have written before about WhatsApp as a hospital’s front door for domestic enquiries. Almost everything in that piece still applies. What follows is the part that is genuinely different when the person messaging you is in another country, in another time zone, in another language, with no way to walk in and check whether you are real.
Why the first reply to an international enquiry decides the case
Of everything an international desk does, the single action with the most influence on whether a case happens is the first reply. Not the website, not the accreditation wall, not the consultant’s record. The message that goes back to a worried family within the first few hours of them writing to you, on whatever channel they chose.
A family enquiring from abroad rarely writes to one hospital. They write to several in an evening, often across more than one country, frequently on WhatsApp, sometimes through a facilitator at the same time. At this point they are not comparing clinical quality. They are finding out which of these places is real and responsive. One reply arrives quickly, from a named person, in a language they read easily, acknowledging what they actually sent and saying what happens next. Another arrives two days later asking them to fill in a form. A third never arrives. The family has ranked three hospitals without knowing anything about their medicine.
From that moment the first good responder has an advantage that is very hard to overturn, because every later message is read against theirs. That is why I treat the reply not as an administrative step but as the product demonstration. Most hospital first replies fail in the same three ways: they are slow, they are generic, and they ask for information the family already sent. Fixing that costs almost nothing and moves more cases than any campaign I have seen.
What the family is doing in the hour after they write
Picture the other side. Somebody has finally persuaded an elder that treatment abroad is worth considering, photographed a set of printed reports on a kitchen table and sent a short message that understates how worried they are. Then they wait, and while they wait they search: the hospital name, the doctor, a relative abroad asked to look too, perhaps an AI assistant. A reply that arrives in that window lands next to everything else they are finding, and it is the only evidence that is about them specifically. Two days later, they have moved on, not because they decided against you but because someone else started a conversation.
The person who wrote is usually not the patient. It is a son, a daughter or a nephew with the best English or the best phone, who will be asked repeatedly and anxiously whether anyone has replied. Every hour without an answer makes that person look ineffective in front of their family. Replying quickly does something for them personally, and they remember it.
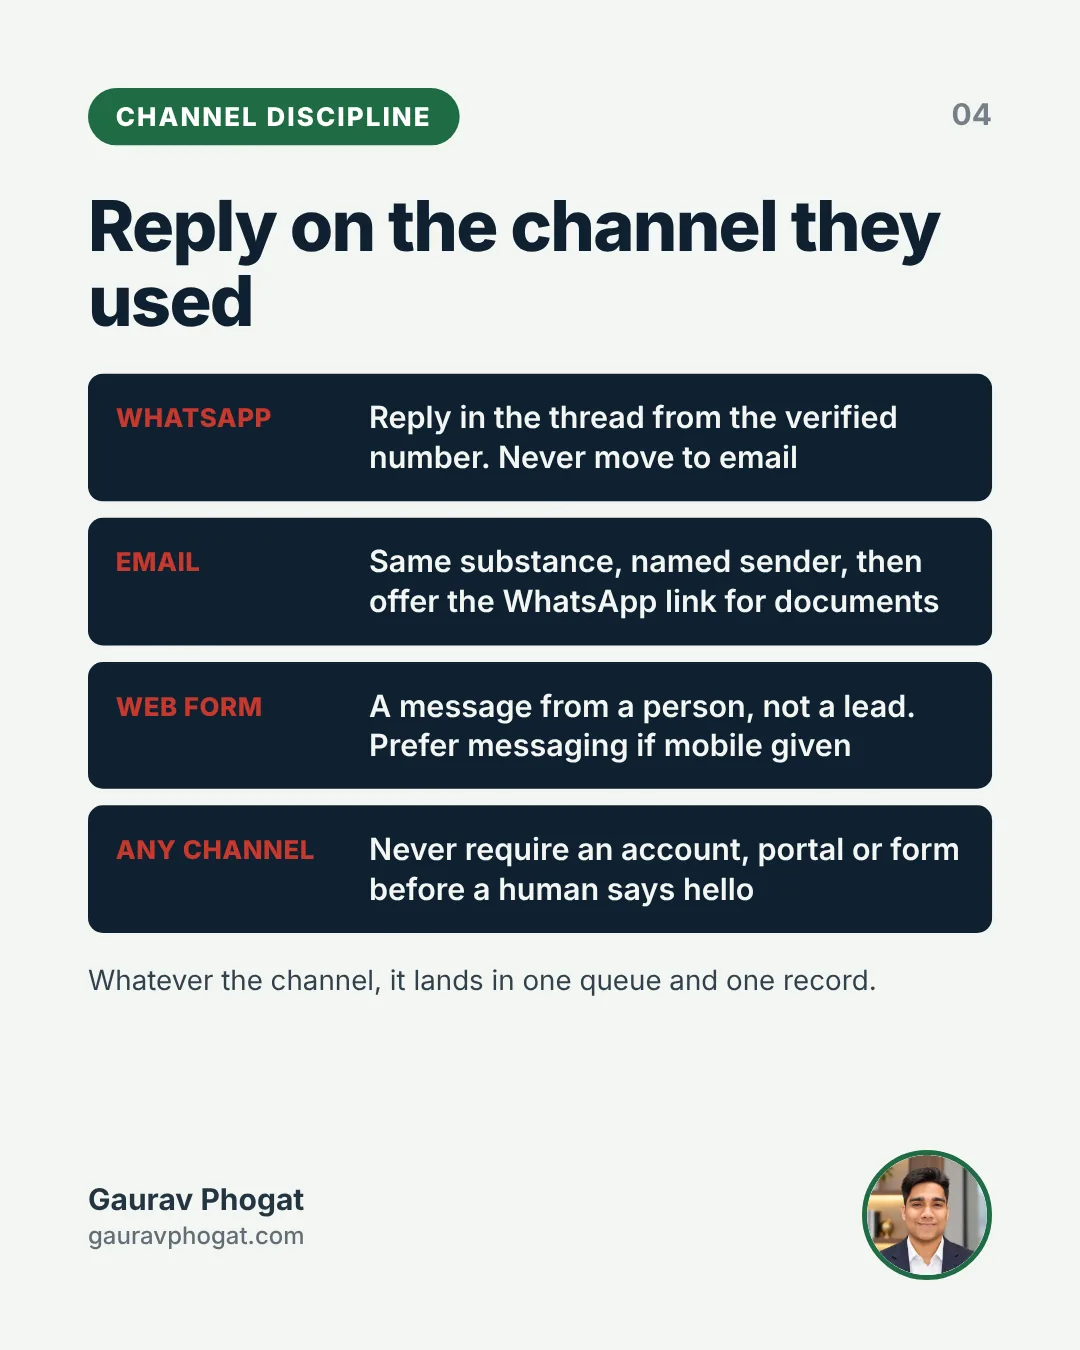
Answer on the channel they used: WhatsApp, email or web form
Channel discipline matters more across a border than it does locally. For most source markets the channel will be WhatsApp, which is why the rest of this guide centres on it. But enquiries also arrive by email, through the website form, by phone and through facilitators, and the rule is the same for all of them: reply first on the channel the family used, then offer to continue wherever is most practical for documents.
- WhatsApp enquiry: reply in the thread, from the verified business number. Do not move a family who messaged you onto formal email, where attachments behave differently on a phone and your message may never be seen.
- Email enquiry: reply by email with the same substance and a named sender, then offer the WhatsApp number as a tappable link for documents and quick questions.
- Web form: treat it as a message from a person, not a lead to be processed. Reply on whichever contact they gave, preferring messaging if they left a mobile number with a country code.
- Any channel: never require an account, a portal or a further form before a human being says hello. A form as a first response reads, correctly, as a hospital protecting its own workflow.
Whatever the channel, the conversation must land in one queue and one record. A family who filled a form and then messaged should not be treated as two strangers by two different agents, and conversations that live on a coordinator’s personal phone are not conversations the hospital owns.
Why WhatsApp for international patients is a different channel
Three things change. The first is asymmetry of trust. A family in your own city can drive past the hospital. A family abroad has only what appears on a screen, so every element of the thread, including the display name, the profile photograph, the grammar and the response time, is being read as evidence about whether you are a real institution or a middleman.
The second is the shape of the conversation. Domestic threads are short and transactional. Cross border threads run for weeks before anyone travels and for months afterwards. They accumulate documents. They pull in several people: the patient, a spouse, an adult child working in a third country who is paying, sometimes a local doctor, sometimes a sponsor’s office.
The third is cost and habit. In many source markets for medical value travel, a voice call to India is expensive and unreliable, while messaging over a data connection is normal for everything from family news to business. Voice notes matter enormously, because a mother who cannot type a long English message can speak one. If your desk treats voice notes as a nuisance, you are refusing the format half your market prefers.
The number is part of the brand
The single most common failure I see is a channel run on coordinators’ personal phones. It works, right up until it does not. The coordinator leaves and takes the relationship, the history and the documents with her. Two coordinators give two different answers on two numbers. Nothing reaches the CRM. Nobody can audit what was promised. And the family has no way to tell whether the number they were given belongs to the hospital at all.
Use one official business number per hospital or per international desk, verified, with a complete business profile: the legal hospital name, the address, the website, working hours stated with the time zone. Verification is not cosmetic. For a family who has been warned about fraud, the difference between a verified business profile and an unknown number is the difference between replying and not replying.
Publish that one number everywhere the market sees you, in international format with the country code, as a tappable link rather than text to copy. Resist the urge to run a separate number per market. It fragments the record, confuses the family who was given a different number by a referring doctor, and multiplies the cost of keeping profiles accurate. One number, several agents behind it, routed by language and market.
When a coordinator does need a direct thread with a family, it should still run through the official number as an assigned conversation, not a personal handset. The relationship belongs to the hospital.
How do you cover international enquiries across time zones?
Your desk works Indian hours. Your markets do not. East Africa is a little behind you, West Africa more so, Central Asia close, the Caucasus and eastern Europe further, and the Pacific islands are effectively a day away. Some of your markets treat Friday as the day nothing happens, others treat Sunday that way, and public holidays in a source market will empty your enquiry flow for a week if you do not know they are coming.
Two decisions follow. First, roster deliberately rather than by accident: stagger the desk so the busiest hours of your two or three largest markets are covered by someone who speaks the language, and accept that this means early mornings or late evenings for somebody. Second, be honest in the automatic reply. An auto reply that says a team will respond shortly, sent at two in the morning their time, tells the family nothing. An auto reply that states your working hours in their time zone and when they can expect a human answer is far better, and far easier to keep.
Speed matters most on the first message, because that is when the family is messaging several hospitals at once. What a good first reply to an international enquiry contains, set out below, is worth settling as a policy rather than leaving to whoever is on shift. After the first reply, consistency beats speed: a family will wait if they know when the answer is coming.
Speed is not the same as being first
It is tempting to solve the first reply with automation alone. An instant acknowledgement beats silence, and automated triage that routes an enquiry to the right specialty and language is genuinely useful. But an instant reply that carries none of the substance below simply proves that a machine answered. What matters is time to first useful human response, and that is a staffing question: a rota, a shared arrangement with the contact centre, or a published response window you actually keep. The worst outcome is an implied promise of constant availability and a real answer on Tuesday morning.
The seven things the first reply has to carry
A good first reply is short and does a specific job. It is not a brochure and it is not a quotation. On WhatsApp, email or anywhere else, it should carry:
- A human name and role, and a way to reach that person directly.
- Confirmation of what you received and understood, in their terms: the patient’s age bracket, the condition as they described it and the documents they sent.
- The language position, made obvious by writing in the family’s language rather than announcing that you can.
- Exactly what you need next, listed precisely, with a reason for each item, and nothing you already have.
- What happens after that, including who will look at the reports and roughly how long an opinion takes.
- An honest position on money: a written estimate follows the clinical opinion, it will state what is included and excluded, and you will not give a casual figure before then. The estimate is a discipline of its own.
- One practical reassurance about the stay, usually about attendants, because it is the worry nobody asks about first.
That is a reply a coordinator can write in a few minutes with good tooling, and it answers more of the family’s real questions than a twenty page brochure. It helps to know which decisions the family is working through at this moment, set out in the five decisions before a country is chosen.
What the first reply must never do
- Offer a clinical view from someone not qualified to give one. A coordinator saying a condition is treatable, that surgery will be needed or how long recovery takes is making a clinical claim on behalf of the hospital. When the consultant later says something different, the family concludes somebody misled them. The opposite failure, a hedge that says the doctor will explain everything after admission without saying what the doctor needs or when, reads as evasion.
- Give a price casually. A figure mentioned in a chat, without scope or conditions, becomes the number the family raises money against and remembers at discharge. If a family insists, explain why a real estimate needs the reports first and say when they will get one.
- Ask for what they already sent. Nothing signals a disorganised hospital faster. It usually happens because the enquiry arrived on one channel and the reply is being written from another system, which is a plumbing problem the CRM-based desk solves.
Templates, translation and the human name
Templates are not the enemy; unedited templates are. The structure of the reply should be standard so it is consistent across coordinators and shifts, and the specifics must be genuinely specific, because that is the only part the family reads closely. Machine translation is good enough to draft with and still not good enough to send unchecked in a high-stakes message, so the practical arrangement is machine draft, review by someone fluent, and a library of reviewed phrases.
Keep the human name real. A shared mailbox signature tells the family nobody in particular is responsible for them, which is the fear they already have. When the coordinator changes across shifts or leave, name the person taking over, say why, and have them show they have read the history rather than asking the family to repeat it.
Language in a written channel
Written language is harder than spoken language for most people, including your agents. A coordinator who handles a phone call in Arabic confidently may write it slowly and with errors. A family may read English well but write it badly, or write their own language in Latin script.
Build a library of approved message templates in each language you support, covering the recurring moments: acknowledgement, what documents to send, how an estimate is produced, what happens on arrival, admission instructions, and follow up after discharge. Have them written by a native speaker and reviewed by the desk, so an agent is composing from correct building blocks rather than translating on the fly at midnight.
Accept voice notes both ways. A coordinator who replies to a long voice note with a short spoken answer in the family’s language does more for trust than any brochure. Where you do not have the language in house, bring an interpreter into the workflow rather than leaving an agent to improvise with a translation app. The decision about which languages you can genuinely support belongs with the design of a multilingual international patient desk, not with the channel.
One rule I would not bend: no clinical opinion in chat from anyone who is not a clinician. Agents collect, describe the process and route. They do not interpret a scan, comment on a diagnosis or say whether surgery is needed, however directly they are asked and however long the family has been waiting.
Reports, photographs and the record
Almost every international case begins with medical records arriving as photographs. Blurry, partial, rotated, taken in poor light, sometimes in a language nobody at your desk reads. This is not a problem to complain about. It is the normal condition of the channel, and your process should assume it.
Tell the family exactly what you need, in plain words and in their language: which pages of which report, the most recent ones first, the scan images if they have them on a disc or a portal, and the doctor’s own note. Ask for one file at a time if the connection is weak. Give a simple naming instruction. When something is unreadable, say what specifically is missing rather than asking them to send everything again.
Then get it out of the phone. Every document, and the key facts around it, belongs in the patient record and the CRM, attached to an enquiry that has a source country, a language, a specialty and an owner. This is the unglamorous heart of the thing, and it is why an international desk that runs on your CRM outperforms one that runs on goodwill. A thread on a phone is not a record. It cannot be reported, audited or handed over.
The same applies in the other direction. Documents you send matter: the estimate, the appointment confirmation, admission instructions, and later the discharge paperwork. Send them as proper documents rather than screenshots, because the family will forward them to a sponsor, an employer, a referring doctor or an authority, and a screenshot of a screenshot is worth nothing to any of them.
Why are international WhatsApp cases lost at handover?
A single international case passes through more hands than a domestic one: first responder, market coordinator, clinical coordinator, the consultant’s secretary, admissions, billing, the arrival team, and after discharge whoever handles follow up. Each handover is a point where the family has to repeat themselves, and each repetition costs confidence.
Fix it with three habits. Keep one thread per case, not one per topic, so the history travels. Introduce the next person inside the thread by name and role before they take over, rather than letting a stranger appear mid conversation. And write a short internal summary at each handover in the CRM, so the person picking it up knows what has been promised without reading forty messages.
Group threads deserve a decision. Families will want the son abroad and sometimes the local doctor in the conversation, which is genuinely useful. It also means clinical and financial information is visible to people who have not consented and may not be entitled to it. My practice is to keep the main thread with the named contact, ask explicitly before adding anyone, and record who is authorised to receive what.
After discharge the thread should not simply stop. The family is going home to a doctor who was not part of any of this, and the handover that matters most is the paperwork: the discharge summary the home country doctor can act on, sent as a document, in a form that travels.
Consent and privacy across a border
Personal and health data collected from a family abroad still sits under your obligations here. Under DPDP you need a stated purpose, a consent you can evidence, a retention position and a way for someone to withdraw. Collect consent in the language of the conversation, in plain words, and log it against the enquiry rather than leaving it in a chat bubble.
Be careful with the ordinary habits of a busy desk: screenshots shared in internal groups, reports forwarded to personal numbers, patient photographs kept on a coordinator’s phone. Those are the breaches that actually happen. Devices used for the channel should be managed, agents should have no ability to export the media library, and access should end the day someone leaves.
Say plainly in the thread what you will do with the reports and who will see them. Families are more willing to share when they are told, and the hospital is in a far better position later if a question is ever asked.
Measuring a channel that does not look like a funnel
Web style metrics mislead here. Sessions and click through rates tell you nothing about a conversation that runs for two months. Measure first response time in the family’s own daytime, not in yours. Measure how many enquiries arrive with usable reports attached, because that is a test of your instructions rather than of your agents. Measure the time from first message to estimate sent, and from estimate to a decision either way.
Then measure the gap everyone avoids: enquiries that produce an estimate but never an arrival, by market and by reason. Some of that is price, some is paperwork, some is a competitor replying faster, and some of it is a family who was never going to travel. You cannot fix it without naming it. Report by source market, never in aggregate, because one market’s pattern says nothing about another’s.
Measuring the first reply
Three measures tell you more than most programmes know. Time to first human response, by market and by hour of arrival, so the gaps show instead of a flattering average. The share of first replies that contain a named person, a specific acknowledgement and a clear next step, which you only know by reading a sample every month with the desk in the room. And the share of enquiries that reply to your reply, because a family that responds is still choosing you. Read the replies, not the dashboard: every growth leader who does this for an afternoon finds something a report would never show.
One caution. The moment time to first response becomes an individual target, coordinators will send something fast and empty to stop the clock. Measure content alongside speed, and count a thin reply sent in minutes as a miss. The arithmetic from enquiry to arrival can be worked through with the enquiry to appointment funnel calculator, adapted for a journey that ends in an arrival.
What I would fix in the first week
Move the channel onto one verified business number and take it off personal phones. Rewrite the automatic reply so it states working hours in the family’s time zone and when a human will answer. Publish the number, in international format, on every international page and in every profile. Agree the language cover for your two largest markets and roster to it. Build the first dozen message templates in those languages and have a native speaker check them.
Then make one rule stick: every document that arrives in the thread goes into the record the same day, and every enquiry carries a source country and an owner. That single habit converts a phone full of conversations into something the hospital can manage, report on and improve. Everything else in this article is easier once it is true.
Before any of that, pull the last set of international enquiries from every channel and look at what actually went back, with timestamps. Most teams find the delay is not where they assumed and the content is worse than they assumed. Rewrite one reply structure covering the seven elements, have it properly translated for your two largest source markets, and agree in writing that nobody outside the clinical team offers a clinical view and nobody outside a defined role offers a figure. None of it needs a budget approval, and it will change your arrivals before any campaign you launch this quarter does.
Further reading from primary sources
- WhatsApp Business Messaging Policy: opt-in rules for messaging people.
- DPDP Rules, 2025 (Press Information Bureau): India’s notified data protection rules and timeline.
- Government of India: e-Visa (including e-Medical and e-Medical Attendant visas): the official source families should check for visa rules.
Questions people ask
Also worth reading: Patients from Bhutan and Myanmar: small volumes, long relationships.
It is the use of a verified business messaging number as the main contact channel for patients enquiring from outside the country, covering the first enquiry, collection of medical reports, the estimate discussion, travel and admission instructions, and follow up after the patient returns home. It differs from domestic use because it carries a long relationship across time zones, languages and borders rather than a quick booking.
Domestic threads are short and transactional. Cross border threads run for weeks before travel and months after, collect documents, and involve several people including a relative in a third country who may be paying. Language, time zone cover, identity verification and the handling of medical records all become central. The underlying setup is the same; the operating discipline around it is not.
No. One verified business number per hospital or international desk, with agents behind it routed by language and market. Personal numbers lose the history when someone leaves, produce inconsistent answers, keep documents out of the record and give families no way to confirm they are talking to the hospital. Assigned conversations give coordinators a direct relationship without the number being theirs.
Roster around your two or three largest markets rather than trying to cover the world. Stagger shifts so the busiest hours in those markets meet someone who speaks the language, and be honest in the automatic reply about your working hours stated in the family’s time zone. Predictability matters more than constant availability; families wait willingly when they know when an answer comes.
Only the ones you can answer in reliably, in writing as well as speech. Written language is harder than spoken, so an agent comfortable on a call may struggle in chat. Approved templates in each supported language, written by native speakers, let agents compose from correct building blocks. Where a language is not available in house, bring an interpreter into the workflow rather than relying on translation apps.
No, and the rule has to be absolute. Agents collect information, explain the process and route the case. They do not interpret scans, comment on a diagnosis or say whether a procedure is needed, however directly they are asked. Clinical answers come from a clinician, through the route the hospital has agreed, and the family should be told plainly when that will happen.
Assume photographs taken in poor light, because that is what arrives. Tell the family exactly which pages and which reports you need, in their language, and ask for one file at a time on a weak connection. Move every document into the patient record and the CRM the same day, attached to an enquiry that carries a source country, language, specialty and owner.
The same obligations apply to a family abroad as to a patient here: a stated purpose, consent you can evidence, a retention position and a way to withdraw. Collect consent in the language of the conversation and log it against the enquiry. The practical risks are internal habits, such as screenshots in staff groups and reports forwarded to personal phones, so manage the devices and end access when people leave.
Keep one thread per case so history travels, introduce the next person by name and role inside the thread before they take over, and write a short internal summary at each handover so nobody has to read the whole conversation. Most lost cases are not lost on price. They are lost when a family has to explain everything again to a stranger.
Often yes, because the relative paying or advising is genuinely part of the decision. Do it deliberately rather than by drift: ask the named contact before adding anyone, and record who is authorised to receive clinical and financial information. Group threads make it easy for sensitive details to reach people who never consented, and that is worth a moment of friction to prevent.
First response time in the family’s daytime rather than yours, the share of enquiries arriving with usable reports, time from first message to estimate, and time from estimate to decision. Then the honest one: enquiries that reach an estimate but never an arrival, by market and by reason. Report by source market, because one market’s pattern tells you nothing about another’s.
The technical part is quick, usually a few weeks including verification and profile setup. The operating part takes a quarter: agreeing language cover, writing and checking templates, rostering to time zones, moving documents into the record and training the desk on handover. The channel starts paying back almost immediately, but the discipline around it is what makes the gains hold.
Mostly people rather than technology. You need enough agents with the right languages at the right hours, someone who owns templates and quality, and a CRM that can hold the record. Messaging platform costs are modest against the value of a single international case, and the bigger cost of getting it wrong is the enquiry that quietly goes to whoever replied more carefully.
No, they feed it. Pages and forms are where a family finds you and decides to make contact; the messaging thread is where the relationship is built. The important thing is that every entry point lands in the same queue with the same record, so a family who filled a form and then messaged is not treated as two strangers by two different agents.
A named person and how to reach them, confirmation of what you received and understood, the reply written in the family’s own language, a precise list of what you still need and why, what happens next and roughly how long an opinion takes, an honest statement that a written estimate follows the clinical review, and one practical reassurance about attendants and the stay.
Not a real one, and a casual figure is worse than none. Families raise money against whatever number they are given and remember it at discharge. Explain that a written estimate follows the clinical review of the reports, say when it will arrive, and describe what it will cover. That answer is usually accepted when it is delivered confidently.
The one they used. Answer an email by email and a WhatsApp message in the thread, then offer to continue wherever suits document exchange, usually WhatsApp. Never require a form, portal or account before a person says hello, and make sure every channel lands in one queue and one record so nobody is asked twice.
Read my takes first in Google Search
